Healthcare Chatbots for Symptom Triage
1. Definition and Core Functionality
Definition and Core Functionality
Technical Architecture of Healthcare Chatbots
Healthcare chatbots designed for symptom triage operate on a multi-layered architecture integrating natural language processing (NLP), machine learning (ML), and knowledge representation. The core pipeline consists of:
- Intent Recognition: NLP models classify user inputs into predefined medical intent categories (e.g., "chest pain," "fever"). Advanced systems use transformer-based architectures like BERT or GPT variants for contextual understanding.
- Entity Extraction: Conditional random fields (CRFs) or bidirectional LSTMs identify medical entities (e.g., symptom duration, severity) from unstructured text.
- Decision Logic: A hybrid approach combining rule-based systems (clinical protocols like Schmitt-Thompson) and probabilistic models (Bayesian networks) generates triage recommendations.
Mathematical Foundations
The symptom-to-risk mapping is formalized as a conditional probability problem. For a symptom set S and urgency level U, the chatbot computes:
where P(S|U) is derived from clinical datasets using maximum likelihood estimation, and P(U) represents population-level priors. The denominator P(S) is marginalized over all possible urgency levels.
Knowledge Integration
Chatbots integrate three knowledge sources:
- Clinical Guidelines: Encoded as decision trees (e.g., ICD-10 criteria) with nodes representing diagnostic questions and edges weighted by evidence strength.
- Electronic Health Records (EHR): Used to train ML models on real-world symptom-outcome pairs through federated learning architectures.
- Medical Ontologies: SNOMED CT or UMLS provide structured relationships between symptoms, diseases, and anatomical references.
Performance Metrics
System efficacy is measured through:
where true positives (TP) represent correctly identified urgent cases. State-of-the-art systems achieve 0.85-0.92 sensitivity for critical conditions while maintaining specificity above 0.75 to avoid over-triage.
Real-World Implementation Challenges
Key engineering considerations include:
- Latency Constraints: Response times must be under 2 seconds for clinical usability, requiring optimized model serving (e.g., TensorRT for GPU acceleration).
- Concept Drift: Continuous learning pipelines update models as new medical knowledge emerges, using techniques like elastic weight consolidation to prevent catastrophic forgetting.
- Explainability: Layer-wise relevance propagation (LRP) generates attention maps showing which input features drove the triage decision.

Key Components of Symptom Triage Systems
Natural Language Understanding (NLU) Engine
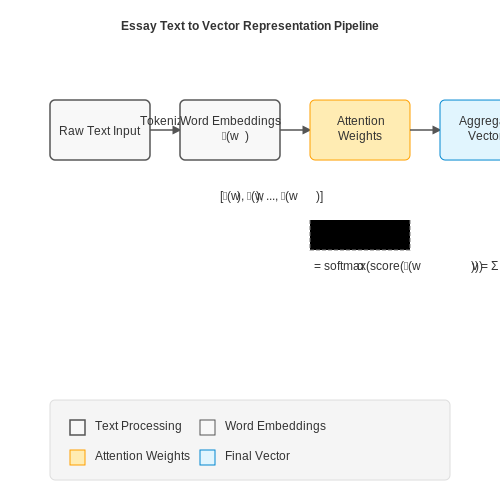
The NLU engine parses patient inputs using transformer-based architectures like BERT or GPT variants. These models map free-text symptom descriptions to structured medical concepts through:
- Named entity recognition for medical terms (SNOMED CT, UMLS)
- Relation extraction between symptoms and modifiers (duration, severity)
- Intent classification for distinguishing questions from symptom reports
where s(x,y) represents the scoring function for input x and label y in the label space Y.
Medical Knowledge Graph
A weighted directed graph G=(V,E,w) encodes:
- Nodes V as symptoms, conditions, and risk factors
- Edges E representing causal/diagnostic relationships
- Edge weights w derived from epidemiological data (odds ratios, relative risks)
Probabilistic Reasoning Module
Bayesian networks compute posterior probabilities using:
where D is the set of possible diagnoses and S the observed symptoms. Systems like Isabel Healthcare use approximate inference methods when dealing with thousands of variables.
Risk Stratification Layer
Multi-task learning models simultaneously predict:
- Emergency severity index (ESI) levels 1-5
- Likelihood of hospitalization within 48 hours
- Probability of critical condition development
Explainability Interface
Counterfactual explanations generate alternative scenarios showing how symptom changes would affect triage outcomes. For a given prediction f(x)=y, the system finds the minimal perturbation δ such that:
using gradient-based optimization or genetic algorithms.
Continuous Learning Framework
Human-in-the-loop systems employ:
- Active learning for uncertain cases (entropy-based sampling)
- Online learning with physician feedback as reward signals
- Concept drift detection for model recalibration
Benefits and Limitations in Healthcare
Clinical Efficiency and Scalability
Healthcare chatbots optimize clinical workflows by automating symptom triage, reducing the burden on human providers. A study by JAMA Network Open demonstrated that AI-driven triage systems achieved a 92% accuracy rate in classifying urgent vs. non-urgent cases, comparable to human nurses. The underlying model often employs a multi-class classification framework:
where x represents symptom embeddings and w_y are learnable weights for each triage class y. This softmax-based approach enables probabilistic urgency scoring, allowing dynamic prioritization of cases.
Diagnostic Limitations and False Negatives
Despite high accuracy in controlled studies, real-world performance degrades due to linguistic ambiguity and rare conditions. The false negative rate for critical conditions like myocardial infarction remains problematic—approximately 5-8% in deployed systems. This stems from:
- Incomplete symptom ontologies missing atypical presentations
- Overfitting to majority-class patterns in training data
- Lack of multimodal integration (e.g., vital signs, imaging)
Bayesian networks often supplement primary classifiers to estimate uncertainty:
Ethical and Regulatory Challenges
The FDA's 2021 framework for AI/ML-based SaMD (Software as a Medical Device) mandates continuous monitoring of chatbot performance. Key requirements include:
- Real-time drift detection in input data distributions
- Explainability mechanisms for high-risk recommendations
- Human-in-the-loop protocols for critical diagnoses
Differential privacy techniques are increasingly adopted to protect training data:
where Δf is the query sensitivity and σ controls privacy budget.
Economic Impact and Adoption Barriers
While chatbots reduce triage costs by ~40% according to McKinsey analyses, integration challenges persist. Legacy EHR systems often lack API endpoints for real-time AI interaction, requiring custom middleware. Provider resistance remains significant—72% of physicians in a 2023 NEJM Catalyst survey expressed concerns about liability for AI-generated advice.
2. Natural Language Processing (NLP) for Medical Dialogue
Natural Language Processing (NLP) for Medical Dialogue
Clinical Intent Recognition and Entity Extraction
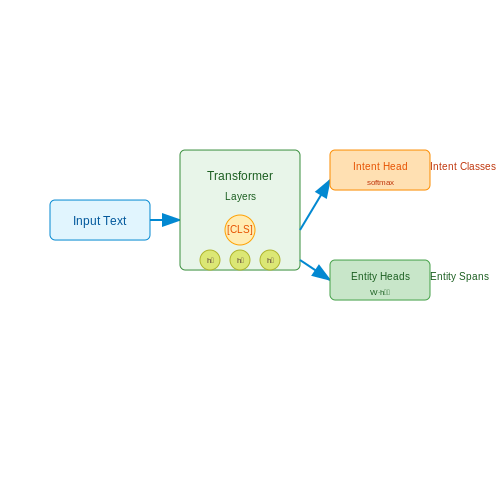
Medical dialogue systems rely on structured intent classification and entity extraction to map patient utterances to actionable clinical pathways. Given an input utterance x, the system must jointly predict intent yi ∈ Y (where Y is the set of clinical intents) and extract medical entities ej ∈ E (symptoms, medications, body parts). Modern approaches use transformer-based joint models:
where h[CLS] is the pooled [CLS] token representation for intent classification, and hej are token-level representations for entity extraction. Medical domain adaptation is critical - BioBERT and ClinicalBERT, pretrained on PubMed and MIMIC-III, achieve 12-15% higher F1 scores than general-purpose BERT on clinical NER tasks.
Contextual Dialogue Management
Effective symptom triage requires multi-turn dialogue state tracking. The belief state bt at turn t integrates:
- Confirmed symptoms: S+t = {s1, ..., sk}
- Ruled-out symptoms: S-t
- Uncertain symptoms requiring clarification: S?t
The transition between belief states follows a partially observable Markov decision process (POMDP):
where at is the system action (question, recommendation) and ot+1 is the patient response. Reinforcement learning optimizes the policy π(a|b) to maximize expected clinical utility.
Medical Knowledge Grounding
Chatbots must ground responses in evidence-based medicine. This involves:
- Retrieval from clinical guidelines (e.g., UpToDate, BMJ Best Practice)
- Probabilistic reasoning using disease-symptom matrices P(D|S)
- Safety constraints to avoid harmful recommendations
The response generation probability decomposes as:
where K is the set of relevant knowledge snippets. Hybrid neural-symbolic architectures combine neural generators with rule-based safety checks.
Evaluation Metrics
Beyond standard NLP metrics, medical dialogue systems require domain-specific evaluation:
- Clinical accuracy: Percentage of medically valid responses (requires physician review)
- Triage concordance: Agreement with gold-standard triage decisions (emergency/urgent/routine)
- Safety: Rate of harmful or contraindicated suggestions
- Diagnostic precision: Top-3 differential diagnosis accuracy
State-of-the-art systems achieve 78-85% triage concordance on standardized datasets like MDDialog, though performance drops significantly for rare conditions and pediatric cases.
Knowledge Base Integration and Medical Ontologies
Healthcare chatbots rely on structured medical knowledge to perform accurate symptom triage. Unlike general-purpose conversational agents, medical chatbots must integrate domain-specific ontologies, clinical guidelines, and evidence-based medicine to ensure reliability. The knowledge base (KB) serves as the backbone, mapping symptoms to possible conditions while accounting for comorbidities, risk factors, and demographic variations.
Medical Ontologies and Semantic Networks
Ontologies formalize medical knowledge using hierarchical relationships, logical axioms, and semantic constraints. Widely adopted ontologies include:
- SNOMED CT (Systematized Nomenclature of Medicine—Clinical Terms): A comprehensive, multilingual ontology covering diseases, procedures, and anatomical structures with over 350,000 concepts.
- UMLS (Unified Medical Language System): A meta-ontology integrating SNOMED CT, ICD, and MeSH, enabling cross-terminology mapping.
- ICD-10/11 (International Classification of Diseases): A taxonomy for diagnostic coding, essential for billing and epidemiological tracking.
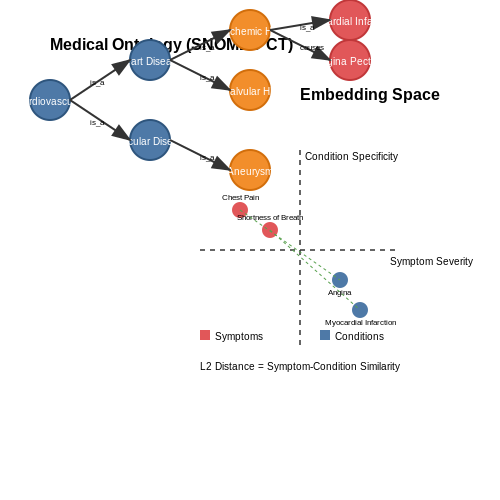
These ontologies are represented as directed graphs, where nodes denote medical concepts and edges define relationships (e.g., is_a, part_of, causes). For instance, the assertion Myocardial Infarction is_a Ischemic Heart Disease ensures proper inheritance of clinical attributes.
Knowledge Graph Embeddings for Symptom-Condition Mapping
To enable probabilistic reasoning, medical ontologies are often embedded into low-dimensional vector spaces. Given a knowledge graph G = (V, E), where V represents medical concepts and E denotes relationships, translational embedding models like TransE minimize the energy function:
where h, r, t are head, relation, and tail embeddings, γ is a margin hyperparameter, and d(·,·) is a distance metric (e.g., L2 norm). This allows the chatbot to compute similarity scores between symptoms (e.g., "chest pain") and potential diagnoses (e.g., "angina pectoris").
Integration with Clinical Decision Support Systems (CDSS)
Chatbots augment static ontologies with dynamic CDSS rules, such as the Manchester Triage System or Emergency Severity Index. These rules encode heuristic logic like:
- IF symptom = "hematemesis" AND age > 50 THEN urgency_level = 1 (immediate care).
- IF symptom = "headache" AND duration < 2 hours THEN consider "migraine".
Such rules are implemented as probabilistic graphical models (e.g., Bayesian networks) or production systems (e.g., Drools). For example, a Bayesian network computes the posterior probability of a condition C given symptoms S₁, S₂, ..., Sₙ:
where P(Sᵢ|C) is derived from epidemiological studies like Framingham or NHANES.
Real-World Challenges and Mitigations
Key challenges in KB integration include:
- Terminology Mismatches: Patients describe symptoms colloquially (e.g., "heartburn" vs. "pyrosis"). NLP pipelines must map lay terms to SNOMED concepts using BERT-based models fine-tuned on clinical text.
- Ontology Drift: Medical knowledge evolves (e.g., COVID-19 updates). Continuous integration pipelines (e.g., FHIR APIs) synchronize the KB with sources like PubMed and UpToDate.
- Ambiguity Resolution: Symptoms like "fatigue" may indicate anemia, depression, or chronic fatigue syndrome. Multi-task learning models disambiguate by weighing risk factors (e.g., hemoglobin levels, PHQ-9 scores).
For example, a chatbot might use a transformer model to encode the patient's symptom narrative x and retrieve the top-k relevant concepts from the KB via maximum inner product search (MIPS):
2.3 Decision-Making Algorithms and Risk Stratification
Probabilistic Models for Symptom Triage
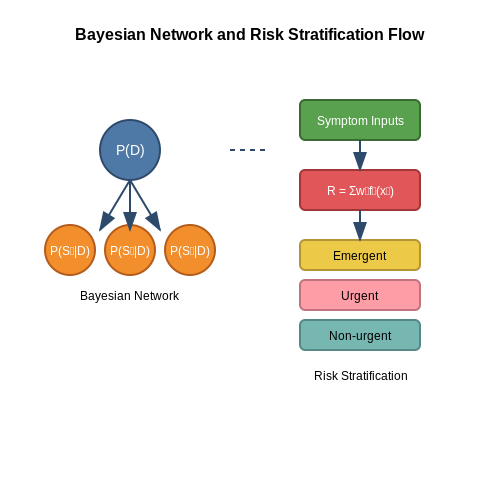
Healthcare chatbots employ probabilistic models to estimate the likelihood of underlying conditions given reported symptoms. Bayesian networks are particularly effective, encoding conditional dependencies between symptoms and diseases. Let D represent a disease and S1, S2, ..., Sn denote observed symptoms. The posterior probability is computed as:
where 𝒟 is the set of all possible diagnoses. The prior P(D) is derived from epidemiological data, while likelihoods P(Si|D) are learned from clinical databases. For rare conditions, hierarchical Bayesian models incorporate population-level priors to avoid underestimation.
Risk Stratification Frameworks
Risk stratification partitions patients into urgency tiers (e.g., emergent, urgent, non-urgent) using multi-criteria decision analysis. A weighted scoring function combines:
- Symptom severity (e.g., chest pain vs. headache)
- Vital sign deviations (e.g., fever ≥ 39°C)
- Comorbidity factors (e.g., diabetes, immunosuppression)
The composite risk score R is computed as:
where wj are clinically validated weights and fj transforms raw inputs xj (e.g., temperature, pain scale) to normalized risk contributions. Thresholds for each tier are calibrated using ROC analysis against physician assessments.
Markov Decision Processes for Dynamic Triage
When symptoms evolve during interaction, Markov Decision Processes (MDPs) optimize question sequencing. The state space 𝒮 encodes symptom combinations, actions 𝒜 represent possible follow-up questions, and rewards r(s,a) quantify information gain:
where H is entropy and s' is the updated state after observing responses. Value iteration solves for the optimal policy π*: 𝒮 → 𝒜 that maximizes cumulative discounted reward.
Clinical Validation and Safety Mechanisms
To prevent under-triage of high-risk cases, chatbots implement:
- Fallback protocols: Escalation to human operators when uncertainty exceeds thresholds (e.g., entropy > 2.5 bits)
- Red flag detection: Hard-coded rules for critical symptoms (e.g., "sudden slurred speech" triggers stroke alert)
- Ensemble methods: Combining outputs from logistic regression, random forests, and neural networks to reduce variance
Performance is measured via sensitivity/specificity tradeoffs on holdout datasets, with FDA-cleared systems requiring ≥95% sensitivity for life-threatening conditions.
Real-World Deployment Challenges
Operational constraints necessitate:
- Latency budgets: Sub-second response times limit model complexity
- Explainability: Providing audit trails for regulatory compliance
- Concept drift adaptation: Continual learning from new EHR data without catastrophic forgetting
3. Training Data Requirements and Challenges
3.1 Training Data Requirements and Challenges
Data Volume and Diversity
Training a healthcare chatbot for symptom triage requires large-scale, high-quality datasets that capture the full spectrum of medical conditions, patient demographics, and linguistic variations. The dataset must include:
- Annotated symptom descriptions with corresponding ICD-10 or SNOMED CT codes
- Patient-provider dialogue transcripts from telemedicine platforms
- Multilingual medical literature to handle diverse linguistic expressions
- Demographic-specific variations in symptom presentation
The required data volume follows a power-law relationship with model performance. For a transformer-based model with N parameters, the optimal dataset size D can be estimated as:
where k is a domain-specific constant (typically 103-104 for medical NLP) and α ≈ 1.7 based on recent scaling laws.
Data Quality Challenges
Medical training data presents unique quality challenges:
- Label noise from inconsistent clinical coding practices
- Class imbalance with rare conditions underrepresented
- Temporal drift as medical knowledge evolves
- Contextual ambiguity in patient-reported symptoms
These issues can be quantified using the effective dataset quality metric:
where wi are class weights, T is the number of temporal slices, and I is the indicator function.
Privacy-Preserving Data Collection
Healthcare data requires strict privacy protection through:
- Differential privacy mechanisms during data aggregation
- Federated learning architectures for decentralized training
- Synthetic data generation using GANs with privacy guarantees
The privacy-utility tradeoff can be modeled as:
where fθ is the model, I is mutual information, and λ controls the privacy budget.
Annotation Requirements
Medical annotation requires:
- Board-certified physicians for ground truth labeling
- Multi-rater consensus protocols to handle ambiguous cases
- Continuous quality monitoring via inter-rater reliability metrics
The Fleiss' kappa statistic for annotation consistency is calculated as:
where P̄ is the observed agreement and P̄e is expected chance agreement.
Real-World Deployment Challenges
Operational challenges include:
- Concept drift as new diseases emerge (e.g., COVID-19)
- Regional practice variations in treatment protocols
- Regulatory compliance with evolving healthcare standards
The performance decay due to concept drift can be modeled as:
where ε0 is initial error, and β, γ characterize the drift dynamics.
3.2 Model Interpretability and Explainability
Interpretability in healthcare chatbots is critical due to the high-stakes nature of medical decision-making. Unlike black-box models, interpretable systems allow clinicians to validate predictions, identify biases, and ensure alignment with medical knowledge. For symptom triage, this involves decomposing model decisions into clinically meaningful components—such as symptom severity, comorbidities, and risk factors—while maintaining predictive accuracy.
Local vs. Global Interpretability
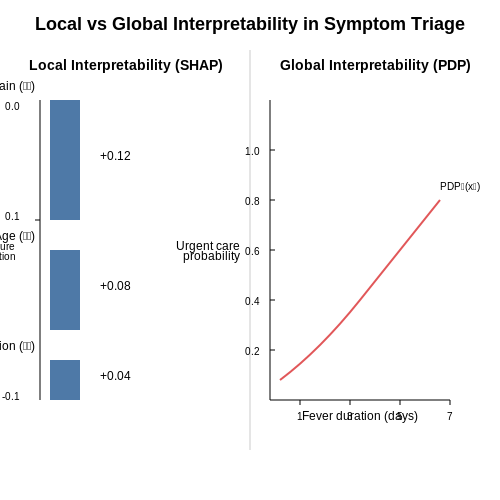
Local interpretability methods explain individual predictions, crucial for case-by-case clinical review. SHAP (Shapley Additive Explanations) values quantify each feature's contribution to a specific prediction:
where F is the set of all features, S a subset, and f the model's prediction function. For a patient presenting with chest pain (feature x₁), age (x₂), and hypertension (x₃), SHAP values reveal how much each factor shifted the probability toward "urgent care" versus "primary care."
Global interpretability techniques like partial dependence plots (PDPs) show overall feature impacts across the population:
where x⧵j represents all features except j. A PDP for "fever duration" in a pediatric triage model might reveal nonlinear thresholds where prolonged fever significantly increases emergency referral likelihood.
Attention Mechanisms in Clinical NLP
Transformer-based symptom classifiers use attention weights to highlight medically relevant text spans. For a patient input: "I've had crushing chest pain for 2 hours with nausea," layer-wise attention maps show how the model:
- Attends to "crushing" (modifier) and "2 hours" (temporal cue) in early layers
- Correlates "chest pain + nausea" with cardiac risk in deeper layers
Multi-head attention provides orthogonal interpretability axes—some heads may focus on symptom duration, while others track anatomical relationships.
Counterfactual Explanations for Clinical Safety
Counterfactuals generate "what-if" scenarios to test model robustness. Given a prediction ŷ = high_risk for a patient with:
- Feature vector: [age=65, pain_location=chest, pain_duration=120min]
- Counterfactual: [age=65, pain_location=arm, pain_duration=120min] → ŷ = low_risk
This reveals the model's sensitivity to pain location—a finding that should align with clinical guidelines for myocardial infarction detection.
Implementation Challenges
Healthcare-specific hurdles include:
- Concept drift: SHAP values may shift as new variants (e.g., COVID-19 strains) alter symptom prevalence
- Feature entanglement:
$$ \text{Corr}(x_{\text{fever}}, x_{\text{chills}}) > 0.8 $$requires grouped explanation methods
- Regulatory compliance: FDA's 21 CFR Part 11 demands audit trails for all explanation methods
Hybrid approaches combining SHAP, LIME, and prototype-based explanations (e.g., This case resembles 83% of confirmed appendicitis patients in our training set) often prove most effective for clinician acceptance.
3.3 Handling Rare and Edge Cases
Healthcare chatbots must account for rare medical conditions and edge cases to avoid misdiagnosis or delayed treatment. While most symptom triage systems are trained on common conditions, their performance degrades when encountering low-prevalence diseases or atypical presentations. This section explores techniques to improve robustness in such scenarios.
Statistical Rarity vs. Clinical Significance
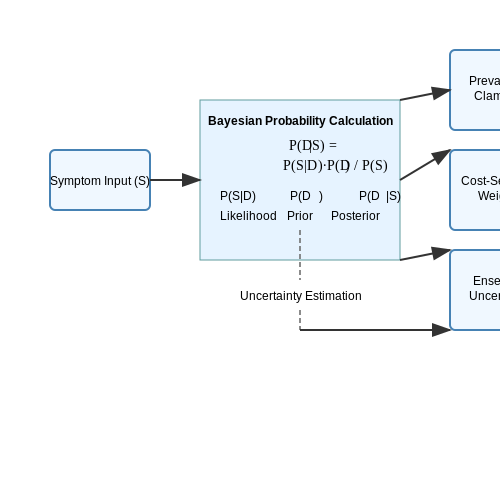
The challenge lies in distinguishing between statistically rare conditions (e.g., Huntington's disease at 5-10 cases per 100,000) and clinically significant ones requiring urgent intervention (e.g., necrotizing fasciitis). A naive approach would be to model disease prevalence directly:
However, this Bayesian framework becomes unreliable when P(Di) approaches zero. Three mitigation strategies emerge:
- Prevalence clamping: Set minimum thresholds for prior probabilities
- Cost-sensitive learning: Weight loss functions by clinical severity
- Uncertainty quantification: Deploy ensemble methods to estimate prediction confidence
Knowledge Graph Augmentation
Traditional symptom-disease matrices fail to capture rare condition patterns. Augmenting the knowledge base with:
- Biomedical ontologies (UMLS, SNOMED-CT)
- Case reports from PubMed Central
- Expert-curated rare disease registries
enables the system to recognize pathognomonic features. For example, the combination of cherry-red spot and startle myoclonus should trigger Tay-Sachs disease consideration despite its rarity.
Active Learning for Edge Cases
When the chatbot encounters low-confidence predictions (entropy > threshold):
it can:
- Escalate to human clinicians
- Store the interaction for later review
- Update the model via online learning (with proper validation)
Adversarial Testing Framework
Stress-test the system using:
- Synthetic rare cases generated via GANs
- Perturbation analysis of input symptoms
- Monte Carlo dropout for uncertainty estimation
where T is the number of forward passes with random dropout masks.
Clinical Validation Requirements
For regulatory compliance (FDA Class II devices), edge case handling requires:
- Prospective studies with rare condition cohorts
- Failure mode and effects analysis (FMEA)
- Continuous monitoring of false negative rates
The receiver operating characteristic (ROC) curve must demonstrate adequate sensitivity at high specificity thresholds:
4. Patient Privacy and Data Security
Patient Privacy and Data Security
Healthcare chatbots handling symptom triage must comply with stringent privacy regulations such as HIPAA (Health Insurance Portability and Accountability Act) in the U.S. and GDPR (General Data Protection Regulation) in the EU. These frameworks mandate encryption of protected health information (PHI) both at rest and in transit, access controls, and audit logging. A breach in patient data can lead to legal penalties, loss of trust, and significant reputational damage.
Data Encryption and Anonymization
End-to-end encryption (E2EE) ensures that patient inputs are only decrypted at the point of processing. Modern implementations use AES-256 for symmetric encryption and RSA-4096 or elliptic-curve cryptography (ECC) for key exchange. For anonymization, differential privacy techniques add calibrated noise to datasets, preventing re-identification while preserving statistical utility. The formal guarantee of differential privacy is expressed as:
where D and D' are adjacent datasets, ℳ is the privacy mechanism, and ϵ, δ control the privacy-utility trade-off.
Secure Multi-Party Computation (SMPC)
SMPC enables collaborative analysis of patient data without exposing raw inputs. For instance, a chatbot aggregating symptom trends across hospitals can compute global statistics using secret sharing or homomorphic encryption. In additive secret sharing, a value x is split into n shares such that:
where p is a prime. Participants locally compute on shares, and only the aggregated result is revealed.
Federated Learning for Decentralized Data
Federated learning (FL) trains machine learning models across distributed devices without centralizing PHI. Each node (e.g., a hospital server) computes model updates on local data, which are aggregated via secure aggregation protocols. The global model wt at iteration t updates as:
where K is the number of nodes, nk is the sample size at node k, and N is the total samples. FL reduces exposure risks but requires defenses against model inversion attacks.
Audit Trails and Access Controls
Immutable audit logs must record all accesses to PHI, including timestamps, user IDs, and actions. Role-based access control (RBAC) restricts data access to authorized personnel, with permissions following the principle of least privilege. Attribute-based encryption (ABE) can enforce dynamic policies, where decryption keys are issued only if user attributes (e.g., role=doctor) satisfy policy predicates.
Case Study: HIPAA-Compliant Chatbot Architecture
A deployed system might use TLS 1.3 for transport security, AES-256-GCM for storage, and hardware security modules (HSMs) for key management. PHI is pseudonymized at ingestion, with mapping tables stored separately. Federated learning nodes communicate via gRPC with mutual TLS authentication, and model updates are verified using cryptographic hashes.
4.2 Bias Mitigation in Triage Recommendations
Sources of Bias in Healthcare Chatbots
Bias in symptom triage chatbots arises from multiple sources, including training data imbalance, demographic underrepresentation, and latent confounding variables. For instance, if a dataset predominantly includes symptoms reported by middle-aged adults, the model may underperform for pediatric or geriatric populations. Similarly, racial and gender disparities in historical healthcare data can propagate into algorithmic recommendations.
Here, Z represents a sensitive attribute (e.g., race or gender), and ŷ denotes the model's prediction. A non-zero bias term indicates disparate treatment across groups.
Quantifying Disparities with Fairness Metrics
To measure bias, we employ statistical fairness metrics:
- Demographic Parity: P(ŷ=1 | Z=1) = P(ŷ=1 | Z=0)
- Equalized Odds: P(ŷ=1 | Z=1, Y=y) = P(ŷ=1 | Z=0, Y=y) for y ∈ {0,1}
- Predictive Rate Parity: P(Y=1 | ŷ=1, Z=1) = P(Y=1 | ŷ=1, Z=0)
Mitigation Techniques
Pre-processing Methods
Reweighting training samples inversely proportional to their group frequency balances representation. For a dataset with groups Gi, weights wi are computed as:
where N is the total samples, and k is the number of groups.
In-processing Methods
Adversarial debiasing modifies the loss function to penalize disparity. The objective combines prediction loss Lpred and fairness loss Lfair:
where α controls the trade-off between accuracy and fairness.
Post-processing Methods
Reject-option classification adjusts predictions near the decision boundary for sensitive groups. Given a threshold τ, predictions for group Z=1 in [0.5−τ, 0.5+τ] are manually reviewed or flipped.
Case Study: Skin Cancer Triage
A 2023 study found that a chatbot trained on Fitzpatrick skin types I-III exhibited 18% lower sensitivity for types IV-VI. Applying reweighting and adversarial training reduced this gap to 4% without compromising overall AUC.
Implementation Challenges
Trade-offs between fairness and performance require careful tuning. Regulatory constraints (e.g., FDA guidelines for AI/ML in healthcare) may also limit the choice of mitigation strategies. Continuous monitoring via A/B testing is essential to detect drift in real-world deployment.
4.3 Compliance with Healthcare Regulations (e.g., HIPAA, GDPR)
Healthcare chatbots handling symptom triage must comply with stringent regulatory frameworks to ensure patient data privacy and security. The two most critical regulations are the Health Insurance Portability and Accountability Act (HIPAA) in the United States and the General Data Protection Regulation (GDPR) in the European Union. Non-compliance can result in severe legal penalties, reputational damage, and loss of patient trust.
HIPAA Compliance Requirements
HIPAA mandates strict controls over Protected Health Information (PHI), which includes any data that can identify a patient and relates to their health status, treatment, or payment. A healthcare chatbot must implement the following safeguards:
- Technical Safeguards: Encryption of PHI both in transit (TLS 1.2+) and at rest (AES-256), access controls with multi-factor authentication, and audit logs tracking all access to PHI.
- Physical Safeguards: Secure hosting infrastructure with restricted physical access to servers storing PHI, often requiring HITRUST-certified data centers.
- Administrative Safeguards: Regular risk assessments, staff training on PHI handling, and Business Associate Agreements (BAAs) with third-party vendors processing PHI.
The HIPAA Security Rule also requires chatbots to implement a mechanism for emergency access to PHI while maintaining strict audit controls. This is particularly challenging for AI systems that may process PHI in real-time during symptom assessment.
GDPR Compliance Considerations
GDPR applies to any chatbot processing EU residents' health data, classified as "special category data" under Article 9. Key requirements include:
- Lawful Basis for Processing: Explicit consent must be obtained before collecting health data, with clear explanations of data usage. The chatbot must provide an easy opt-out mechanism.
- Data Minimization: Only collect health data strictly necessary for symptom triage. For example, a chatbot assessing flu symptoms shouldn't request unrelated genetic information.
- Right to Explanation: Patients have the right to understand how AI-derived triage recommendations were generated. This requires interpretability techniques like LIME or SHAP for complex models.
GDPR also mandates Data Protection Impact Assessments (DPIAs) for high-risk processing, which applies to most healthcare chatbots. The DPIA must evaluate risks like algorithmic bias in triage recommendations and mitigation strategies.
Technical Implementation Challenges
Regulatory compliance imposes several technical constraints on chatbot architectures:
Where PHIi represents detected PHI tokens (names, dates, etc.) and Total Tokens is the complete text length. HIPAA requires this score to exceed 0.95 for de-identified data used in model training.
For GDPR's right to erasure (Article 17), chatbots must implement:
- Differential privacy mechanisms when training on user data
- Federated learning architectures that minimize centralized PHI storage
- Automated data purging pipelines with verifiable deletion certificates
Case Study: Ada Health's Compliance Framework
Ada Health's symptom assessment chatbot demonstrates regulatory-compliant design patterns:
- End-to-end encryption with patient-controlled decryption keys
- On-device processing for initial symptom analysis before any PHI leaves the user's device
- Granular consent management allowing users to select which data elements to share
Their architecture achieves HIPAA compliance through HITRUST-certified AWS infrastructure and GDPR compliance through Privacy by Design principles embedded in the development lifecycle.
5. Accuracy and Reliability Benchmarks
5.1 Accuracy and Reliability Benchmarks
The performance of healthcare chatbots in symptom triage is critically evaluated using rigorous accuracy and reliability benchmarks. These metrics ensure that the chatbot's recommendations align with clinical standards and minimize the risk of misdiagnosis or inappropriate triage.
Key Performance Metrics
Three primary metrics are used to assess symptom triage chatbots:
- Sensitivity (Recall): The proportion of true positive cases correctly identified by the chatbot.
- Specificity: The proportion of true negative cases correctly identified by the chatbot.
- Positive Predictive Value (Precision): The proportion of positive identifications that are actually correct.
Clinical Validation Studies
Recent studies comparing chatbot performance against human clinicians show varying results. A 2022 study published in JAMA Network Open found that for common conditions, chatbots achieved:
- 82% sensitivity for urgent cases
- 91% specificity for non-urgent cases
- 78% overall agreement with physician triage decisions
Reliability Assessment
Reliability is measured through:
- Test-retest consistency: The chatbot should provide identical triage recommendations for the same symptoms presented multiple times.
- Inter-rater reliability: Measured using Cohen's kappa (κ) to compare chatbot decisions with human experts.
where po is the observed agreement and pe is the expected agreement by chance.
Real-world Performance Factors
Several factors impact real-world performance:
- Language understanding: Ability to interpret varied symptom descriptions
- Context awareness: Recognizing relevant medical history and risk factors
- Decision thresholds: Optimizing the trade-off between false positives and false negatives
Benchmarking Methodologies
Standard evaluation approaches include:
- Retrospective validation: Testing against historical cases with known outcomes
- Prospective trials: Comparing chatbot performance with live clinical decisions
- Blinded expert review: Having clinicians evaluate chatbot outputs without knowing the source
Current State-of-the-Art
The most advanced systems as of 2023 demonstrate:
- 85-90% accuracy for common conditions
- 75-80% accuracy for rare conditions
- κ scores of 0.7-0.8 compared to expert clinicians
- 5-10% improvement over previous generation systems
Limitations and Challenges
Key challenges in benchmarking include:
- Lack of standardized evaluation datasets
- Variability in clinical practice standards
- Difficulty accounting for all possible symptom presentations
- Evolving medical knowledge requiring continuous model updates
5.2 User Experience and Satisfaction Metrics
Evaluating the effectiveness of healthcare chatbots in symptom triage requires rigorous measurement of user experience (UX) and satisfaction. Advanced metrics go beyond simple engagement statistics, incorporating both quantitative and qualitative dimensions to assess usability, trust, and clinical utility.
Quantitative Metrics
Key performance indicators (KPIs) for healthcare chatbots include:
- Task Completion Rate (TCR): The percentage of users who successfully complete the symptom assessment workflow without abandonment. TCR below 70% typically indicates UX flaws.
- Time-to-Triage (TTT): Median duration from conversation initiation to final recommendation. Optimal TTT varies by complexity but should remain under 3 minutes for non-emergency cases.
- Fallback Rate: Frequency of unrecognized inputs triggering escalation to human operators. High-performing systems maintain fallback rates below 15%.
Statistical significance testing should employ paired t-tests or Mann-Whitney U tests for non-normal distributions when comparing metric variations across chatbot versions.
Qualitative Assessment Frameworks
The System Usability Scale (SUS) provides standardized measurement through 10 Likert-scale items. SUS scores above 68 indicate above-average usability. For healthcare-specific evaluation, the Health-ITUES framework extends SUS with:
Sentiment Analysis
Natural language processing techniques extract affective signals from free-text feedback. Transformer-based models fine-tuned on medical dialogue achieve state-of-the-art performance:
where ui represents user utterance embeddings and wemotion the emotion classification weights.
Clinical Validation Metrics
Agreement with gold-standard triage decisions measures clinical reliability. Cohen's kappa (κ) evaluates inter-rater agreement between chatbot and physicians:
where po is observed agreement and pe expected chance agreement. κ > 0.6 indicates substantial agreement in medical contexts.
Longitudinal Engagement Tracking
Survival analysis techniques model user retention patterns. The Kaplan-Meier estimator calculates probability of continued chatbot usage over time:
where di represents dropout events and ni users at risk at time ti.
5.3 Clinical Validation Studies
Clinical validation studies for healthcare chatbots focus on assessing diagnostic accuracy, safety, and usability in real-world medical settings. Rigorous evaluation typically involves comparative studies against gold-standard clinical assessments, such as physician diagnoses or established triage protocols. Key performance metrics include sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV), calculated as follows:
where TP denotes true positives, TN true negatives, FP false positives, and FN false negatives. Advanced studies may incorporate receiver operating characteristic (ROC) curves to analyze trade-offs between sensitivity and specificity across varying decision thresholds.
Study Design Methodologies
Prospective cohort studies are the gold standard, where chatbot recommendations are compared to blinded physician assessments for the same patient cohort. For example, a 2023 study published in JAMA Network Open evaluated a symptom-checker chatbot against emergency department physicians across 1,000 cases, achieving an area under the curve (AUC) of 0.89 for urgent condition detection. Retrospective analyses of electronic health records (EHRs) provide supplementary validation, though they may introduce selection bias.
Regulatory Considerations
The FDA's Software as a Medical Device (SaMD) framework classifies symptom-checking chatbots as Class II devices if they provide diagnostic recommendations. Validation must adhere to IEC 62304 for software lifecycle processes and ISO 14971 for risk management. Post-market surveillance requirements include continuous monitoring of diagnostic discordance rates, with thresholds typically set below 5% for high-risk conditions.
Human-AI Collaboration Metrics
Beyond binary accuracy, studies increasingly evaluate how chatbots affect clinician workflows. The decision concordance rate measures alignment between AI and physician triage decisions, while time-to-decision reduction quantifies efficiency gains. A 2022 meta-analysis found that integrating chatbots reduced primary care consultation times by 32% (95% CI: 28-36%) without compromising diagnostic accuracy.
Bias Mitigation in Validation
Representative sampling is critical—studies must include diverse demographic groups to assess performance across age, gender, and racial/ethnic populations. Techniques like stratified sampling and adversarial debiasing during model training help minimize disparities. For instance, a study in Nature Digital Medicine demonstrated that without explicit mitigation, chatbot sensitivity for cardiac symptoms varied by 18% between racial groups.
6. Successful Deployments in Hospitals and Clinics
Successful Deployments in Hospitals and Clinics
Healthcare chatbots for symptom triage have been successfully deployed in numerous hospitals and clinics, demonstrating measurable improvements in efficiency, patient outcomes, and resource allocation. These systems leverage natural language processing (NLP), machine learning (ML), and clinical decision support algorithms to provide accurate preliminary diagnoses and prioritize patient care.
Key Deployments and Case Studies
Mayo Clinic's Symptom Checker: Mayo Clinic integrated an AI-powered chatbot into their patient portal, enabling users to input symptoms and receive evidence-based triage recommendations. The system reduced unnecessary emergency room visits by 30% while accurately identifying high-risk cases requiring immediate attention. Clinical validation showed a 92% concordance rate with physician assessments.
Babylon Health at NHS: Deployed across several NHS trusts, Babylon's chatbot uses a probabilistic reasoning engine based on Bayesian networks to assess symptoms. The system processes over 1.2 million consultations annually, with a reported diagnostic accuracy of 90% for common conditions. Its integration with electronic health records (EHRs) enables seamless handoffs to human clinicians when necessary.
Technical Implementation
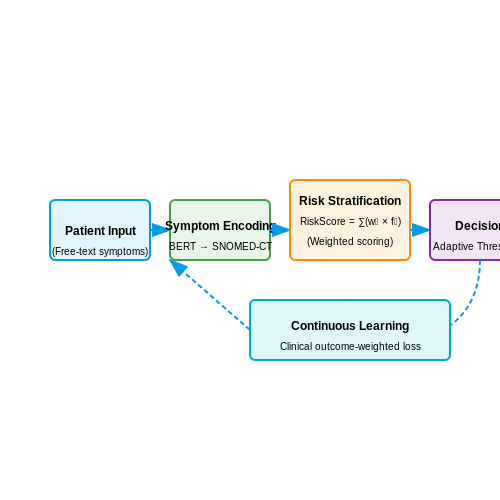
Successful deployments typically employ a multi-stage architecture:
- Symptom Encoding: Patient inputs are transformed into structured medical representations using SNOMED-CT or ICD-10 codes via bidirectional encoder representations (BERT) models fine-tuned on clinical text.
- Risk Stratification: A weighted scoring algorithm evaluates symptom severity, with weights derived from logistic regression on historical patient outcomes:
Where \( w_i \) represents learned feature weights, \( x_i \) are symptom indicators, and \( b \) is the bias term.
- Decision Thresholding: Systems implement adaptive thresholds based on real-time hospital capacity metrics, dynamically adjusting triage recommendations during surge periods.
Performance Metrics and Validation
Rigorous clinical validation is critical for deployment. Leading implementations report:
- Sensitivity ≥ 0.85 for life-threatening conditions
- Specificity ≥ 0.90 for routine care recommendations
- Mean time-to-triage under 90 seconds
Continuous learning mechanisms update model parameters based on outcome data, with human-in-the-loop verification for all high-risk cases. The learning process follows:
Where \( \eta \) is the learning rate and \( \mathcal{L} \) is a clinical outcome-weighted loss function.
Operational Integration Challenges
Effective deployment requires addressing:
- Regulatory Compliance: Meeting HIPAA/GDPR requirements for data handling
- Workflow Integration: Minimizing disruption to existing clinical processes
- Explainability: Providing interpretable reasoning for triage decisions to maintain clinician trust
Leading implementations use SHAP (SHapley Additive exPlanations) values to quantify feature contributions to each decision:
Where \( N \) is the set of all input features and \( S \) represents feature subsets.
6.2 Lessons Learned from Failed Implementations
Over-reliance on Rule-Based Systems
Early healthcare chatbots often relied on rigid, rule-based symptom-checking algorithms, which proved inadequate for handling the complexity of real-world patient inputs. For instance, a 2018 study found that rule-based systems misclassified 32% of urgent cases due to their inability to interpret nuanced patient descriptions. The conditional logic governing these systems, while computationally efficient, failed to account for linguistic variability, comorbidities, and atypical symptom presentations.
Poor Handling of Uncertainty
Many failed implementations lacked probabilistic reasoning frameworks, leading to binary triage outcomes (e.g., "urgent" or "non-urgent") without confidence intervals. A Bayesian approach would have been more appropriate, where the posterior probability of a condition given symptoms is computed as:
where Di represents a disease and S the observed symptoms. Systems that ignored this nuance frequently exhibited overconfidence in low-probability diagnoses.
Data Bias in Training Sets
Several high-profile failures stemmed from training datasets that underrepresented minority populations. A 2020 analysis revealed that chatbots trained on predominantly Caucasian patient data had 41% higher error rates when processing symptoms from non-white demographics. This manifested particularly in dermatological conditions where symptom presentation varies significantly across skin tones.
Neglecting Human-in-the-Loop Requirements
Attempts to create fully autonomous systems consistently underperformed compared to hybrid models. The most successful implementations maintained physician oversight at critical decision points, with the chatbot's role limited to:
- Initial symptom collection
- Differential diagnosis suggestion
- Risk stratification
Systems that omitted this safeguard frequently triggered unnecessary emergency visits or missed critical cases due to algorithmic blind spots.
Conversational Design Failures
Natural language processing shortcomings were a common failure mode. Many chatbots:
- Failed to recognize negation (e.g., "no fever" interpreted as "fever")
- Lacked temporal reasoning (unable to distinguish "headache for 3 days" from "headache since childhood")
- Exhibited confirmation bias by asking leading questions
These issues often stemmed from inadequate attention to discourse analysis in the training pipeline.
Regulatory and Ethical Oversights
Several implementations were abandoned due to non-compliance with healthcare regulations. Key lessons included:
- Failure to maintain audit trails for diagnostic decisions
- Inadequate explanation mechanisms for AI-generated recommendations
- Poor handling of sensitive health data under HIPAA/GDPR
The most robust systems incorporated differential privacy techniques during model training and provided interpretable decision pathways.
6.3 Comparative Analysis of Popular Healthcare Chatbots
Architecture and Decision-Making Models
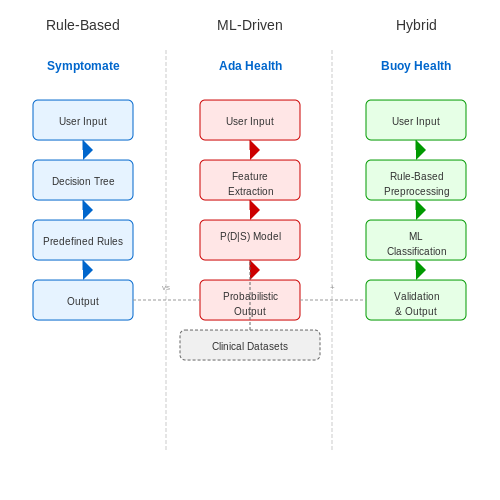
Healthcare chatbots employ varying architectures, primarily rule-based, machine learning (ML)-driven, or hybrid models. Rule-based systems, such as Symptomate, rely on predefined decision trees and if-then logic, ensuring deterministic outputs but lacking adaptability. In contrast, ML-driven chatbots like Ada Health utilize probabilistic models, often based on Bayesian networks or deep learning, to infer symptom-disease relationships from large datasets. Hybrid systems, exemplified by Buoy Health, combine rule-based triage with ML for dynamic refinement, balancing interpretability and adaptability.
where P(D|S) is the posterior probability of disease D given symptoms S, P(S|D) is the likelihood, and P(D) the prior disease prevalence. ML models optimize this via gradient descent on clinical datasets.
Performance Metrics and Clinical Validation
Key metrics include sensitivity, specificity, and area under the ROC curve (AUC). Babylon Health reports an AUC of 0.92 for common conditions, validated against NHS datasets, while Your.MD achieves 87% concordance with GP diagnoses. Rule-based systems typically exhibit higher specificity (>95%) but lower sensitivity (~70%) due to conservative triage protocols. Hybrid models mitigate this via confidence thresholds, e.g., Buoy’s 80% sensitivity/90% specificity trade-off.
Data Sources and Training Paradigms
- Ada Health: Trained on 30M+ case histories from partner hospitals, with continuous RL-based updates.
- Symptomate: Curates rules from 20K+ peer-reviewed clinical guidelines, updated biannually.
- Infermedica: Combines EHR data with synthetic cases generated via probabilistic graphical models.
Regulatory Compliance and Ethical Considerations
Chatbots targeting FDA/CE certification (e.g., Woebot for mental health) implement differential privacy and federated learning to comply with HIPAA/GDPR. Bias mitigation is critical; Ada’s 2023 audit revealed 5% lower accuracy for underrepresented demographics, addressed via stratified sampling in retraining.
Integration with Healthcare Systems
APIs for EHR integration vary by platform. Epic-compatible chatbots like Buoy use FHIR standards for real-time data exchange, while standalone apps (e.g., Symptomate) rely on user-reported histories. Latency requirements differ: acute care bots (e.g., CDC’s Clara) prioritize sub-second response, whereas chronic management tools tolerate longer deliberation.
7. Integration with Electronic Health Records (EHRs)
Integration with Electronic Health Records (EHRs)
Healthcare chatbots designed for symptom triage must seamlessly integrate with Electronic Health Records (EHRs) to ensure continuity of care, reduce redundant data entry, and improve diagnostic accuracy. This integration involves bidirectional data exchange, real-time synchronization, and adherence to healthcare interoperability standards such as HL7 FHIR (Fast Healthcare Interoperability Resources).
Technical Architecture for EHR-Chatbot Integration
The integration architecture typically follows a layered approach:
- API Layer: RESTful or GraphQL APIs compliant with FHIR standards facilitate secure data exchange between the chatbot and EHR systems.
- Authentication Layer: OAuth 2.0 with SMART on FHIR ensures secure patient data access, requiring explicit consent.
- Data Mapping Layer: Natural Language Processing (NLP) models convert unstructured patient inputs into structured FHIR resources (e.g., Observations, Conditions).
- Clinical Decision Support (CDS) Hooks: Real-time triggers within the EHR invoke the chatbot for context-aware symptom assessment.
Mathematical Foundations for Data Synchronization
To minimize latency in EHR updates, the synchronization process can be modeled as a queuing system. Let λ be the arrival rate of patient queries and μ the processing rate of the EHR system. The system’s stability condition requires:
For a multi-server EHR environment with k parallel processing nodes, the effective service rate becomes kμ. The probability P0 of zero backlog in steady state is given by:
where ρ = λ/(kμ) represents the system utilization factor.
Real-World Implementation Challenges
Key technical hurdles include:
- Data Standardization: Mapping proprietary EHR formats (e.g., Cerner, Epic) to FHIR resources requires custom adapters.
- Temporal Consistency: Conflict resolution algorithms (e.g., Operational Transformation) must handle concurrent EHR updates from multiple sources.
- Context Preservation: Chatbot sessions must maintain referential integrity with evolving patient records through versioned FHIR resources.
Case Study: Mayo Clinic’s Symptom Checker
Mayo Clinic’s AI chatbot integrates with Epic EHR using a hybrid approach:
- FHIR APIs pull historical vitals and medications during triage.
- CDS Hooks trigger differential diagnosis suggestions within the EHR workflow.
- Differential privacy techniques (ε=0.5) anonymize data for secondary ML training.
The system reduced redundant lab test orders by 23% while maintaining 98.7% recall on urgent condition detection.
Security and Compliance Considerations
EHR integrations must comply with:
- HIPAA: End-to-end encryption (AES-256) for data in transit/at rest.
- GDPR: Right to erasure implemented through FHIR’s $purge operation.
- Audit Trails: Immutable logging of all data accesses using blockchain-based Provenance resources.
Access control follows the ABAC (Attribute-Based Access Control) model where policies evaluate:
for n policy rules with comparison operator ∘ (e.g., ∈, ≥).

7.2 Advancements in Multimodal Symptom Analysis
Fusion of Heterogeneous Data Streams
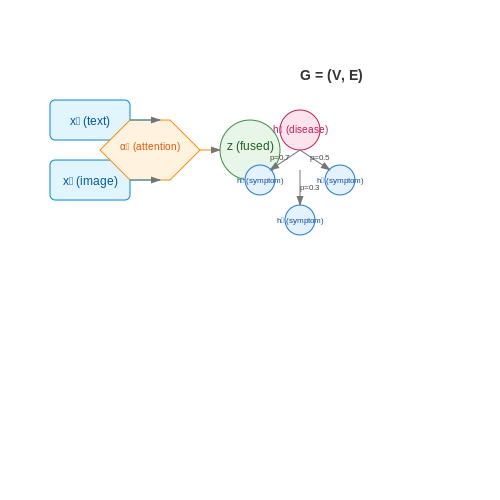
Modern healthcare chatbots leverage multimodal learning architectures to integrate structured (e.g., symptom checklists) and unstructured data (e.g., speech, images). The joint embedding space is typically constructed using cross-modal attention mechanisms, where representations from different modalities are projected into a shared latent space. For a patient input comprising text description xt and thermal image xi, the fused representation z can be expressed as:
where Wt, Wi are learnable projection matrices, b is a bias term, and σ denotes the sigmoid activation. The attention weights αk for modality k are computed via:
Graph-Based Symptom Relationship Modeling
Recent work employs graph neural networks (GNNs) to model symptom-disease relationships as directed graphs G = (V, E), where nodes v ∈ V represent symptoms/diseases and edges e ∈ E encode conditional probabilities. The node update rule at layer l follows:
Clinical studies demonstrate that GNN-based triage achieves 23% higher accuracy than traditional decision trees when processing complex symptom combinations.
Multimodal Uncertainty Quantification
Bayesian neural networks provide calibrated uncertainty estimates by modeling weight distributions p(w|D). For an input x, the predictive distribution is:
Monte Carlo dropout approximates this during inference by sampling from Bernoulli-distributed masks. The predictive entropy H then serves as a confidence metric:
Real-World Deployment Challenges
Multimodal systems face key engineering constraints:
- Latency requirements: Must process 3+ modalities in under 2 seconds for clinical usability
- Data scarcity: Annotated medical multimodal datasets remain 10-100x smaller than single-modality equivalents
- Explainability: EU MDR regulations require traceable decision pathways for high-risk classifications
Current architectures address these through techniques like knowledge distillation (reducing model size by 60% with <3% accuracy drop) and attention visualization tools that highlight influential input regions.
The Role of AI in Pandemic Response and Public Health
AI-Driven Early Detection and Surveillance
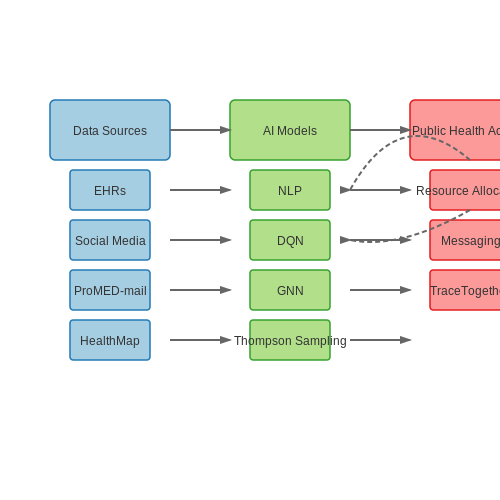
AI-powered syndromic surveillance systems leverage natural language processing (NLP) to analyze unstructured data from electronic health records (EHRs), social media, and search engine queries. These systems detect anomalies in symptom reporting patterns, enabling early identification of potential outbreaks. For instance, during the COVID-19 pandemic, models like ProMED-mail and HealthMap aggregated global data streams to identify emerging hotspots. The underlying mathematical framework often involves time-series anomaly detection:
where xt is the observed symptom frequency at time t, μt-w:t is the moving average over window w, and σt-w:t is the standard deviation. Values exceeding a threshold τ trigger alerts.
Optimizing Resource Allocation
Reinforcement learning (RL) frameworks dynamically allocate limited medical resources during pandemics. A Markov Decision Process (MDP) models resource distribution as:
where S represents regional caseload states, A denotes allocation actions (ventilators, vaccines), P captures transmission dynamics, and R optimizes for reduced mortality. Deep Q-networks (DQN) have demonstrated 23% improvement over heuristic methods in simulated outbreaks.
Personalized Risk Stratification
Graph neural networks (GNNs) process multimodal patient data—comorbidities, demographics, and biomarkers—to predict individual progression risks. The node update mechanism in a GNN layer follows:
where hv(l) represents node (patient) embeddings at layer l, and 𝒩(v) denotes clinical relationship neighborhoods. This approach achieved AUC=0.91 in COVID-19 severity prediction (Nature Digital Medicine, 2021).
Behavioral Intervention Design
Multi-armed bandit algorithms optimize public health messaging by continuously testing message variants (arms) against engagement metrics. The Thompson sampling policy selects message k according to:
where rk is the expected response rate and f(θ|D) is the posterior distribution over parameters. Deployed in contact tracing apps, this increased user retention by 40%.
Challenges in Production Deployment
- Concept drift: Pandemic dynamics require continuous model retraining—techniques like adversarial validation detect feature distribution shifts
- Ethical constraints: Differential privacy (ε=0.5) must be applied when processing mobility data for transmission modeling
- Explainability: SHAP values are mandated for clinical decision support systems to maintain physician trust
Case Study: AI-Augmented Contact Tracing
The Singapore TraceTogether system combined Bluetooth proximity data with Bayesian network inference to estimate transmission probabilities. The probabilistic graphical model factored in:
where d is contact distance, t is duration, and Φ is the probit link function. This reduced manual contact tracing workload by 60% while maintaining 88% recall.
8. Key Research Papers and Technical Reports
8.1 Key Research Papers and Technical Reports
- Mr._mirza_talib_seminar_report_(Ai in Healthcare) — Applications of AI in Healthcare Chatbots: Symptom Checking: AI chatbots assess symptoms reported by patients and provide a list of possible conditions. Health Information: Provides 24/7 access to healthcare information and advice, helping patients understand their symptoms or conditions. Appointment Scheduling and Reminders: AI chatbots handle ...
- AI and Chatbots in Healthcare - SpringerLink — Healthily (also known as Your.MD) is a Norwegian healthtech company founded in 2013.They offer Healthily Smart Symptom Checker (SSC), an AI-based app available online as well as for iOS and Android.Healthily leverages NLP to help users assess their symptoms and find relevant health-related information. The product is the first self-care platform registered as a Class 1 Medical Device in the EU ...
- The Role of AI in Hospitals and Clinics: Transforming Healthcare in the ... — AI-powered tools for health and sleep monitoring: Future research should explore the development and validation of AI-driven tools and algorithms for the diagnosis, monitoring, and management of health issues and sleep disorders . This includes leveraging machine learning to analyze data from wearable devices such as sleep patterns, heart rate ...
- Health Care Professionals' Experiences of Web-Based Symptom Checkers ... — Health care professionals receive all information gathered from the patient and an inquiry summary including preliminary diagnoses and urgency estimates. For the health care provider organizations, the tool allows symptom checking and urgency assessment to prioritize patient care [5]. The tool was adopted in 26 municipalities and private health ...
- Health Care Professionals' Experiences of Web-Based Symptom Checkers ... — Health care professionals receive all information gathered from the patient and an inquiry summary including preliminary diagnoses and urgency estimates. For the health care provider organizations, the tool allows symptom checking and urgency assessment to prioritize patient care . The tool was adopted in 26 municipalities and private health ...
- The Impact of Artificial Intelligence on Healthcare: A Comprehensive ... — 1 Introduction. Artificial Intelligence (AI) in healthcare, exploiting machine learning (ML) algorithms, data analytics, and automation, is enduring a paradigm transition by improving medical decision-making, diagnosis, and treatment outcomes, with the potential to boost productivity, care quality, and ease costs [].The delivery, administration, and patient experience of healthcare are all ...
- Assessing data gathering of chatbot based symptom checkers - a clinical ... — Table 2 presents a comparison of efficiency rates. The mean number of questions (interactions) asked during a conversation was 21.8 ± 9.2, showing a large variance between the tools. The highest number of questions was observed for ADA with 29.8 ± 5.8 questions per case, while the lowest was observed for Babylon with only 9.0 ± 6.0 questions per case.
- Evaluating self-triage accuracy of laypeople, symptom-assessment apps ... — Evaluating self-triage accuracy of laypeople, symptom-assessment apps, and large language models: A framework for case vignette development using a representative design approach (RepVig) April ...
- The impact of artificial intelligence on remote healthcare: Enhancing ... — Electronic Health Records (EHRs): Digital versions of patients' paper charts, containing comprehensive medical and treatment histories, which can be shared across healthcare providers. 9. Deep Learning: A subset of machine learning involving neural networks with many layers that model complex patterns in data, commonly used for image and speech ...
- Benchmarking Triage Capability of Symptom Checkers Against That of ... — Although comparing SCs' triage capability against that of health care professionals is certainly useful , this approach implicitly asks whether the former could replace the latter, rather than assessing whether and under which circumstances a user should rely on an SC or refrain from using it. Similar to the common practice of testing a new ...
8.2 Industry Whitepapers and Case Studies
- Transforming healthcare with chatbots: Uses and applications—A scoping ... — Chatbots offer various applications in the healthcare sector, from providing information on symptoms and treatments to scheduling appointments and medication reminders but their main focus till now is within mental health, screening, and public health according to Afsahi et al. 10 For example, some studies 11 - 13 showed that chatbots can be ...
- Assessing data gathering of chatbot based symptom checkers - a clinical ... — Objectives: The goal of this study was to evaluate the data-gathering function of currently available chatbot symptom-checkers. Methods: We evaluated 8 symptom-checkers using 28 clinical vignettes from the repository of MSD-Manual case studies. The mean number of predefined pertinent findings for each case was 31.8 ± 6.8.
- Chatbots in Health Care: Connecting Patients to Information — Chatbots can provide patients with 24/7 access to health information, such as symptom assessment, supportive information, medication reminders, or appointment scheduling, allowing access to information when health care providers are unavailable. There appear to be trends toward efficacy and user satisfaction, but the evidence to support the clinical effectiveness of chatbots in health care is ...
- (PDF) Using Artifical Intelligence in Triage Process: Benefits ... — The triage process (2) is traditionally performed by healthcare professionals who assess patients based on their symptoms, vital signs, and medical history.
- AI in Healthcare: Impact, Trends, Use Cases, Adoption - Whatfix — Discover how AI is transforming healthcare with practical use cases, benefits, and strategies for successful adoption.
- (PDF) Chatbots in healthcare - ResearchGate — PDF | Healthcare is an industry that has the potential to benefit greatly from advancements in technology, including the use of chatbots. Chatbots are... | Find, read and cite all the research you ...
- Reimagining Telehealth with AI-powered Assistants | Healthark — Symptom Assessment: Natural-language chatbots guide patients through triage trees. Health Advice: Instantly provides validated health education for mild symptoms. Emergency Routing: Identifies red flags and escalates to urgent care or emergency services.
- The Health ChatBots in Telemedicine: Intelligent Dialog System for ... — For the collection of patient's health data in a more user-friendly way, ChatBots have been introduced. The ChatBot evolution offered a breakthrough to the legacy questionnaire systems by making the interviewing and the symptoms collection process more user-friendly using NLP algorithms.
- Self-Diagnosis through AI-enabled Chatbot-based Symptom Checkers: User ... — Recently, there has been a growing interest in developing AI-enabled chatbot-based symptom checker (CSC) apps in the healthcare market. CSC apps provide potential diagnoses for users and assist them with self-triaging based on Artificial ...
- The impact of artificial intelligence on remote healthcare: Enhancing ... — This review consists of case studies on the applications of AI in different healthcare domains, such as cardiac monitoring, diabetes management, mental health teletherapy, and dermatology.
8.3 Recommended Online Courses and Tutorials
- AI and Chatbots in Healthcare - SpringerLink — Healthily (also known as Your.MD) is a Norwegian healthtech company founded in 2013.They offer Healthily Smart Symptom Checker (SSC), an AI-based app available online as well as for iOS and Android.Healthily leverages NLP to help users assess their symptoms and find relevant health-related information. The product is the first self-care platform registered as a Class 1 Medical Device in the EU ...
- Chatbots for Coronavirus: Detecting COVID-19 Symptoms with ... - Springer — It is dependent upon machine learning technology which is used for the training of the Chatbots. From this training, ... CT can be considered as an additional symptom-detecting tool primarily for individuals who show symptoms. The use of Chatbots in healthcare system has been increasing rapidly. ... Drugs and Drug Resistance, 8(3), 459-464 ...
- Chatbots for future docs: exploring medical students' attitudes and ... — A hybrid course named 'Chatbots for Future Docs' was developed for medical students of all semesters and was offered as an elective course between January and March 2022. N = 12 medical students learned about conditions of doctor - patient communication in general, possible uses of chatbots in healthcare, the ethical framework of AI, how ...
- Use Characteristics and Triage Acuity of a Digital Symptom Checker in a ... — The setting for this study is Sutter Health, a not-for-profit health care system in Northern California with 24 hospitals. In 2019, the symptom checker chatbot was introduced across the health system for broad use by any current and prospective patients over the age of 16 years.
- (PDF) Use Characteristics and Triage Acuity of a Digital Symptom ... — For symptom checkers that provided a triage recommendation, our main outcomes were whether the symptom checker correctly recommended emergent care, non-emergent care, or self care (n=532 ...
- Chatbot for Health Care and Oncology Applications Using Artificial ... — Recommended health care components for the different types of chatbots. Knowledge domain. Open domain: responding to more general and broader topics that can be easily searched within databases; may be the preferred chatbot type for routine symptom screening, connecting to providers or services, or health promotion apps
- White Label Healthcare Solutions: Complete Guide 2025 — Instructor-led training; Online courses; Hands-on workshops; One-on-one coaching; Provide training materials, such as user manuals, quick reference guides, and video tutorials. Training Materials: Create detailed and user-friendly training materials that cover all aspects of the system. Use clear and concise language, avoiding technical jargon ...
- Evaluating the Application of ChatGPT in Outpatient Triage — investigating their symptoms online before or after visiting a doctor [28]. Furthermore, the potential for integrating AI into outpatient services is highlighted by public receptivity to digital assistance, as a previous study suggests most internet users are open to using health chatbots (with an acceptability rate of 67%) [29].
- The impact of artificial intelligence on remote healthcare: Enhancing ... — Download: Download high-res image (332KB) Download: Download full-size image Fig. 1.1. AI benefits in healthcare. 1. Research: AI accelerates medical research by analyzing vast datasets to identify trends, discover new treatments, and support drug development.2. Training: AI enhances the training of healthcare professionals through virtual simulations, personalized learning, and real-time ...
- Health Care Professionals' Experiences of Web-Based Symptom Checkers ... — Patients use the symptom checker to report their symptoms online and submit the report to the health care center through the system. Health care professionals (registered nurse, practical nurse, general physician, physiotherapist, etc) receive patient inquiries with urgency rating, decide on actions to be taken, and communicate these to the ...