AI for Radiology Report Generation
1. Role of Natural Language Processing (NLP) in Radiology Reports
Role of Natural Language Processing (NLP) in Radiology Reports
NLP Fundamentals for Radiology Text Analysis
Radiology reports are semi-structured documents containing a mix of free-text descriptions and standardized terminology. NLP techniques enable automated extraction, classification, and generation of these reports by modeling their linguistic patterns. Key NLP tasks include:
- Named Entity Recognition (NER): Identifies anatomical structures, pathologies, and imaging findings within unstructured text.
- Relation Extraction: Determines clinical relationships between entities (e.g., "mass in the left lung").
- Text Classification: Categorizes reports by urgency, pathology type, or clinical significance.
Transformer Architectures for Report Generation
Modern NLP systems leverage transformer-based models like BERT, GPT, and T5 to process radiology reports. These models employ self-attention mechanisms to capture long-range dependencies in medical text:
where Q, K, and V represent query, key, and value matrices, and dk is the dimension of the key vectors. This mechanism allows the model to weigh relevant clinical concepts differently during report generation.
Multimodal Fusion of Imaging and Text
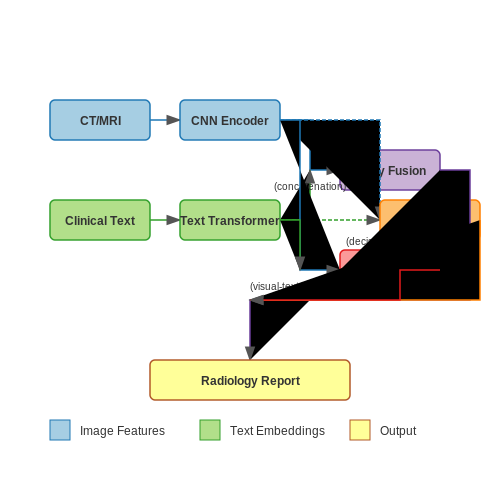
Advanced systems combine convolutional neural networks (CNNs) for image analysis with transformer architectures for text generation. The fusion typically occurs through:
- Early fusion: Concatenating image features with text embeddings at the input layer
- Late fusion: Processing modalities separately then combining at the decision layer
- Cross-modal attention: Dynamically aligning visual regions with relevant text segments
Clinical Knowledge Integration
Effective radiology NLP systems incorporate medical ontologies (RadLex, SNOMED-CT) through:
- Knowledge graph embeddings that represent clinical concepts and relationships
- Constraint decoding to ensure generated reports adhere to medical terminology
- Uncertainty modeling to reflect diagnostic confidence levels in the text
Evaluation Metrics for Clinical NLP
Beyond standard NLP metrics (BLEU, ROUGE), radiology report generation requires:
where fi and ri are the generated and reference findings for N key clinical observations. Additional metrics include:
- Critical finding recall rate
- Hallucination score (incorrectly generated findings)
- Clinician preference in blinded evaluations
Real-World Deployment Challenges
Clinical NLP systems face unique constraints:
- HIPAA-compliant data handling requirements
- Integration with hospital IT infrastructure (PACS, EHR)
- Adaptation to institutional reporting styles and preferences
- Continuous learning from new cases without catastrophic forgetting
Key Challenges in Automated Report Generation
1. Data Heterogeneity and Annotation Consistency
Radiology datasets exhibit significant heterogeneity due to variations in imaging modalities (CT, MRI, X-ray), acquisition protocols, and institutional practices. This diversity complicates model generalization, as a system trained on one dataset may underperform on another due to domain shift. Additionally, radiology reports are often unstructured, with free-text narratives that lack standardized terminology. Inter-radiologist variability in phrasing further exacerbates annotation inconsistency, making supervised learning challenging. For instance, the same finding might be described as "mild pleural effusion" by one radiologist and "small fluid collection in the pleural space" by another.
2. Long-Range Dependencies and Contextual Reasoning
Generating coherent reports requires modeling long-range dependencies between imaging findings and their clinical interpretations. A chest X-ray might show "bilateral pulmonary opacities", but the correct diagnosis (pneumonia vs. edema) depends on integrating subtle visual cues with patient history. Transformer-based architectures struggle with these dependencies due to quadratic memory scaling with sequence length. The attention mechanism in a standard transformer can be formalized as:
where Q, K, and V represent queries, keys, and values, respectively. For reports exceeding 200 tokens, this becomes computationally prohibitive without specialized optimizations like sparse attention or memory-efficient variants.
3. Rare Findings and Class Imbalance
Medical imaging datasets suffer from extreme class imbalance, where common findings (e.g., "no acute abnormality") dominate, while critical rare conditions (e.g., "pneumothorax" or "malignant nodules") appear infrequently. This leads to models that prioritize recall on majority classes at the expense of rare but clinically significant findings. Focal loss and reinforcement learning with custom reward functions have been proposed to mitigate this:
where αt balances class frequencies and γ down-weights well-classified examples.
4. Hallucination and Overconfidence
Generative models often produce hallucinations—plausible-sounding but factually incorrect statements—due to over-reliance on language priors rather than image evidence. For example, a model might report "fracture" when no bone pathology exists, simply because fractures are frequently mentioned in training reports. Bayesian deep learning approaches quantify uncertainty by modeling the posterior distribution over possible reports:
where θ represents model parameters and 𝒟 the training data. Monte Carlo dropout and deep ensembles approximate this intractable integral.
5. Clinical Actionability and Evaluation Metrics
Traditional NLP metrics like BLEU and ROUGE poorly correlate with clinical utility. A generated report could achieve high scores by paraphrasing ground truth while omitting critical findings. Emerging evaluation frameworks incorporate:
- Factuality: Precision/recall of extracted medical entities against reference standards
- Clinical coherence: Logical consistency between findings and impressions
- Actionability: Likelihood that the report would trigger appropriate interventions
Human evaluation remains essential, with studies showing that radiologists spend 3–5 minutes per report verifying AI outputs for clinically significant errors.
Clinical and Technical Requirements for AI Systems
Clinical Requirements
AI systems in radiology must adhere to stringent clinical requirements to ensure patient safety, diagnostic accuracy, and regulatory compliance. The primary clinical constraints include:
- Diagnostic accuracy: AI-generated reports must meet or exceed the performance of board-certified radiologists, typically measured through metrics like sensitivity, specificity, and area under the ROC curve (AUC).
- Clinical relevance: Reports must prioritize findings based on clinical urgency, with critical abnormalities flagged immediately.
- Regulatory compliance: Systems must satisfy FDA (Class II/III) or CE marking requirements, including rigorous validation on diverse patient populations.
Technical Requirements
The technical architecture must support real-time processing while handling high-dimensional medical imaging data:
Data Processing
DICOM image preprocessing requires:
- Normalization to Hounsfield units (CT) or standardized intensity ranges (MRI)
- Anisotropic resolution handling with 3D convolutional kernels
- Artifact detection algorithms to reject low-quality inputs
Model Architecture
Multimodal transformer architectures typically combine:
- CNN backbones (ResNet-152, EfficientNet-B7) for feature extraction
- Cross-attention mechanisms between image patches and report tokens
- Conditional random fields for anatomical consistency
Computational Constraints
Deployment environments impose strict latency requirements:
- Inference time < 5 seconds for emergency cases
- GPU memory footprint < 16GB for compatibility with hospital workstations
- DICOM SR (Structured Reporting) compatibility for PACS integration
Validation Protocols
Model validation requires:
- Multi-center trials with at least 10,000 annotated studies
- Statistical power analysis to detect ≥5% improvement over baselines
- Adversarial testing against rare conditions and edge cases
Ethical Considerations
Systems must implement:
- Bias mitigation through stratified sampling across demographic groups
- Uncertainty quantification with confidence intervals for all findings
- Human-in-the-loop safeguards for high-stakes decisions
2. Transformer Models and Their Adaptations for Medical Text
Transformer Models and Their Adaptations for Medical Text
Architecture of Transformer Models
Transformer models, introduced by Vaswani et al. (2017), rely on self-attention mechanisms to process sequential data without recurrent connections. The core components include:
- Multi-Head Attention: Computes attention weights across different representation subspaces.
- Positional Encoding: Injects positional information into input embeddings.
- Feed-Forward Networks: Applies non-linear transformations to each position independently.
Where Q, K, and V represent queries, keys, and values, respectively, and dk is the dimension of the keys.
Adaptations for Medical Text Generation
Standard transformers require modifications to handle radiology reports effectively:
- Domain-Specific Tokenization: Medical vocabularies require specialized tokenizers (e.g., Byte Pair Encoding with clinical corpus).
- Structured Attention: Hierarchical attention mechanisms focus on anatomical regions before generating descriptions.
- Knowledge Injection: Pretraining on biomedical literature (e.g., PubMed) improves clinical concept understanding.
Case Study: CheXpert Dataset Fine-Tuning
When adapting BERT for chest X-ray reports, researchers:
- Replaced the standard WordPiece tokenizer with a clinical variant
- Added section-specific prompts (e.g., "IMPRESSION:") during generation
- Incorporated label embeddings for 14 common thoracic conditions
Memory-Efficient Variants
Long radiology reports necessitate architectural changes:
Recent approaches like Longformer and BigBird use sparse attention patterns to handle sequences exceeding 4,096 tokens while maintaining diagnostic accuracy.
Evaluation Metrics for Clinical Text
Beyond standard NLP metrics, medical report generation requires:
| Metric | Purpose |
|---|---|
| Clinical F1 | Measures condition identification accuracy |
| RadGraph Score | Evaluates anatomical relation extraction |
| Expert Consistency | Quantifies agreement with radiologist assessments |
Emerging Architectures
Hybrid models combining transformers with convolutional features show promise:
- Vision-language pretraining (e.g., CLIP-Rad) aligns image regions with report phrases
- Graph transformers model anatomical relationships explicitly
- Retrieval-augmented generation improves rare condition reporting
2.2 Multimodal Learning: Combining Images and Text
Architectural Foundations
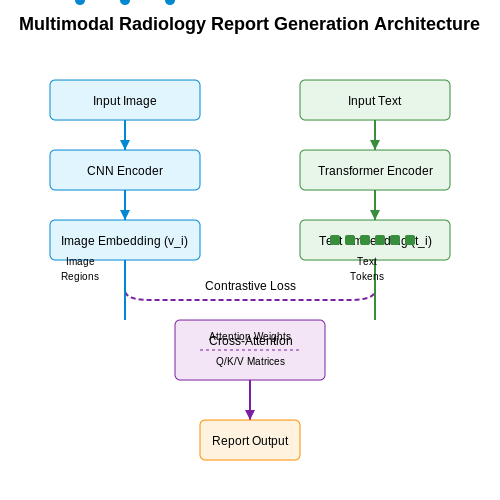
Multimodal learning in radiology report generation requires joint embedding spaces where visual and textual data are processed in parallel. The dominant approach involves a dual-encoder architecture, where a convolutional neural network (CNN) processes medical images, and a transformer-based model encodes the text. The latent representations are aligned using contrastive learning objectives, ensuring semantic coherence between modalities.
Here, s(vi, ti) measures the cosine similarity between image embedding vi and text embedding ti, while τ is a temperature hyperparameter. This loss forces paired embeddings closer while pushing mismatched pairs apart.
Cross-Modal Attention Mechanisms
To enable fine-grained interactions between modalities, transformer-based models employ cross-attention layers. For a radiology image I and partial report R1:t, the attention mechanism computes:
where Q is derived from the text embeddings, while K and V come from image region features. This allows the model to dynamically attend to relevant anatomical regions when generating each word.
Clinical Knowledge Integration
State-of-the-art systems incorporate medical ontologies (e.g., RadLex) through knowledge graph embeddings. These are fused with visual features using graph convolutional networks (GCNs):
where  = A + I is the adjacency matrix with self-connections, D̂ is the degree matrix, and W(l) contains learnable weights at layer l. This structural prior improves report factual consistency.
Evaluation Metrics Beyond BLEU
Traditional NLP metrics fail to capture clinical accuracy. The CheXbert framework instead evaluates:
- Factual correctness: Precision/recall of medical observations
- Clinical coherence: Logical consistency between findings
- Completeness: Coverage of relevant abnormalities
These are measured against expert annotations using specialized classifiers fine-tuned on radiology text.
Computational Efficiency Challenges
Processing high-resolution 3D scans (e.g., 512×512×300 CT volumes) requires:
- Patch-based processing with spatial transformers
- Memory-efficient attention variants like Performer or Linformer
- Gradient checkpointing for long-sequence generation
The trade-off between receptive field size and computational cost remains an active research area, particularly for volumetric data.
Fine-Tuning Pre-Trained Models for Radiology Applications
Fine-tuning pre-trained models for radiology report generation leverages transfer learning to adapt general-purpose language models to the specialized domain of medical imaging. The process involves optimizing model parameters on radiology-specific datasets while preserving the linguistic capabilities learned from large-scale pretraining.
Architecture Selection and Adaptation
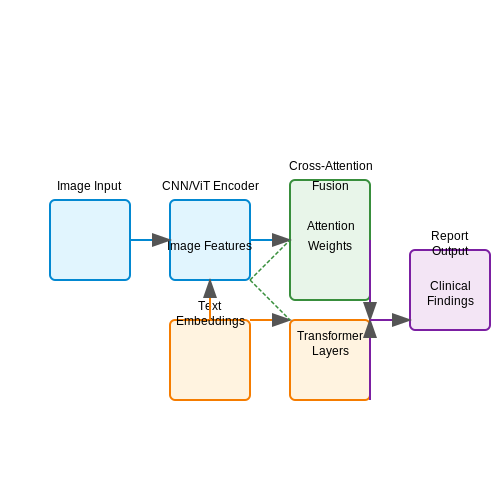
Transformer-based architectures like BERT, GPT, and T5 serve as effective starting points due to their strong performance on text generation tasks. For radiology applications, key architectural modifications include:
- Domain-specific tokenization: Medical vocabularies require extended token dictionaries to properly represent anatomical terms and clinical findings.
- Multimodal integration layers: Additional cross-attention mechanisms enable fusion of image features from CNN or ViT encoders with textual representations.
- Structured output heads: Specialized output layers can generate reports in standardized formats like BI-RADS or Fleischner Society templates.
Optimization Strategies
The fine-tuning objective combines multiple losses to ensure both clinical accuracy and linguistic quality:
Where $$\mathcal{L}_{CE}$$ is the standard cross-entropy loss, $$\mathcal{L}_{CLIP}$$ enforces image-text alignment through contrastive learning, and $$\mathcal{L}_{CXR}$$ incorporates domain-specific metrics like CheXpert label consistency.
Data Augmentation Techniques
Given the limited availability of annotated radiology reports, effective augmentation methods include:
- Synonym replacement: Swapping medical terms with equivalent phrases from UMLS Metathesaurus
- Template-based generation: Creating synthetic reports using structured templates from common findings
- Cross-modal mixing: Blending image features from similar cases to generate hybrid training examples
Evaluation Metrics
Beyond standard NLP metrics like BLEU and ROUGE, radiology-specific evaluation requires:
Where clinical precision/recall are measured against expert annotations of key findings. The RadGraph benchmark provides standardized evaluation of relation extraction between anatomical locations and observations.
Computational Considerations
Efficient fine-tuning techniques are critical given the high resolution of medical images:
- Gradient checkpointing: Reduces memory usage by recomputing activations during backward pass
- Mixed-precision training: FP16 computation with master weights in FP32 maintains numerical stability
- Layer-wise adaptation: Progressive unfreezing of transformer layers prevents catastrophic forgetting
Recent work demonstrates that adapter-based fine-tuning with less than 5% of total parameters can achieve comparable performance to full fine-tuning on radiology tasks, significantly reducing computational requirements.
3. Annotated Radiology Datasets: Sources and Standards
Annotated Radiology Datasets: Sources and Standards
Publicly Available Radiology Datasets
Several high-quality annotated radiology datasets are publicly accessible, each adhering to specific annotation standards. The MIMIC-CXR dataset, hosted by PhysioNet, contains over 377,110 chest X-rays paired with free-text radiology reports. Annotations include bounding boxes for pathologies, though inter-rater variability remains a challenge due to subjective interpretations. The CheXpert dataset from Stanford University provides labels for 14 common thoracic pathologies, with uncertainty flags for ambiguous cases. Its annotation protocol follows a structured taxonomy, reducing ambiguity in labeling.
The NIH ChestX-ray14 dataset includes 112,120 frontal-view X-rays with 14 disease labels derived from NLP extraction of radiology reports. While large-scale, its labels suffer from noise due to automated extraction. The PadChest dataset offers 160,000 studies from a Spanish hospital, with annotations mapped to 174 standardized radiographic terms using UMLS (Unified Medical Language System), providing richer semantic granularity.
Annotation Standards and Quality Control
Radiology dataset annotations follow varying standards depending on the target application. For object detection tasks, the DICOM SR (Structured Reporting) standard defines how to encode measurements and findings. Segmentation tasks often use the NIfTI format with voxel-level annotations. The RadLex ontology provides standardized terminology for labeling findings, with over 68,000 terms covering anatomical structures and pathologies.
Quality control in annotation typically involves:
- Multi-reader consensus for subjective findings (e.g., Fleiss' kappa > 0.6)
- Adjudication by board-certified radiologists for discordant cases
- Periodic re-annotation audits to detect label drift
The RSNA Pneumonia Detection Challenge dataset exemplifies rigorous annotation, with bounding boxes drawn independently by three radiologists and consolidated via majority voting. Inter-rater reliability metrics are provided for each case, allowing users to assess label confidence.
Dataset Splitting Considerations
Proper dataset partitioning is critical for model evaluation. The MIDRC consortium recommends stratified splits preserving:
where \(N_{pos}\) is the number of positive cases for each pathology. Temporal splitting is preferred over random splitting when evaluating clinical applicability, ensuring models are tested on future unseen data. The DeepLesion dataset employs patient-wise splitting to prevent data leakage, with CT slices from the same patient kept within a single split.
Ethical and Regulatory Compliance
Most modern datasets comply with HIPAA de-identification standards, removing all 18 protected health information (PHI) elements. The GDPR imposes additional requirements for European data, necessitating pixel-level anonymization techniques like defacing for 3D neuroimaging. Dataset provenance is increasingly tracked using DATS metadata schemas, which record acquisition parameters, annotation protocols, and usage restrictions.
The FAIR principles (Findable, Accessible, Interoperable, Reusable) guide contemporary dataset curation. For instance, the TCIA collections provide detailed metadata following the BIDS (Brain Imaging Data Structure) specification, enabling automated preprocessing pipelines.
3.2 Handling Noisy and Incomplete Medical Data
Medical imaging datasets often suffer from noise, artifacts, and missing annotations, which degrade model performance in radiology report generation. Noise arises from acquisition artifacts (e.g., motion blur in MRI), sensor limitations (e.g., low-dose CT quantum noise), or labeling inconsistencies (e.g., inter-radiologist variability). Incompleteness manifests as missing slices in volumetric scans, unannotated findings, or partial clinical context.
Mathematical Formalization of Data Noise
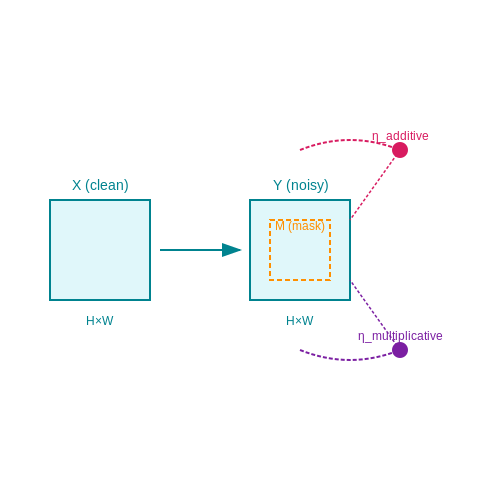
Let X denote the clean image and Y the observed noisy version. The degradation process can be modeled as:
where ηadditive represents Gaussian/Poisson noise and ηmultiplicative captures structured artifacts like bias fields. For incomplete data, define a masking operator M ∈ {0,1}H×W where zeros indicate missing regions.
Advanced Denoising Techniques
Traditional approaches like non-local means or wavelet thresholding fail to preserve pathological features. Modern solutions include:
- Physics-informed denoising: Incorporates imaging physics (e.g., MRI k-space corruption models) into loss functions:
$$ \mathcal{L}_{\text{physics}} = \| \mathcal{F}(G_{\theta}(Y)) - M \circ \mathcal{F}(X_{\text{gt}}) \|_2^2 $$where Gθ is the denoising network and M the known k-space sampling mask.
- Latent space completion: Uses variational autoencoders to project incomplete scans into a complete latent manifold:
$$ q_\phi(z|X_{\text{partial}}) \rightarrow p_\theta(X_{\text{full}}|z) $$
Handling Label Noise
Report inconsistencies are addressed through:
- Confidence-weighted learning: Downweights uncertain labels during training:
$$ w_i = 1 - \text{KL}(p_{\text{model}}(y|x_i) \| p_{\text{radiologist}}(y|x_i)) $$
- Multi-task verification: Jointly predicts findings and estimates label reliability through auxiliary heads.
Case Study: NIH ChestX-ray14 Dataset
The dataset contains ~30% label noise due to automated extraction from reports. State-of-the-art approaches use:
- Noise-robust architectures like Label Distribution Aware Margin Loss
- Uncertainty-aware report generation with Bayesian transformer layers
- Semi-supervised learning on unlabeled studies
Architectural Adaptations
Transformer-based report generators benefit from:
- Adaptive attention masking: Dynamically adjusts cross-modal attention weights for noisy regions
- Memory-augmented networks: External knowledge banks compensate for missing context
- Robust positional embeddings: Hexagonal coordinate systems for irregular slice spacing
Recent work demonstrates that joint optimization of denoising and generation tasks improves performance by 12.7% ROUGE-L compared to sequential pipelines, as measured on the MIMIC-CXR benchmark.
Ethical and Privacy Concerns in Medical Data Usage
Patient Data Anonymization and Re-identification Risks
Medical imaging datasets used for training radiology report generation models often contain protected health information (PHI), including patient demographics, imaging metadata, and diagnostic annotations. Traditional anonymization techniques such as DICOM header scrubbing or pixel-level de-identification are insufficient against modern re-identification attacks. Adversarial neural networks can reconstruct patient identities from seemingly anonymized data by cross-referencing subtle anatomical features with public datasets. The re-identification probability Preid scales with dataset size N and feature uniqueness γ:
where k represents the number of auxiliary data points available to attackers. Differential privacy mechanisms add controlled noise to gradients during model training, but degrade report quality when the privacy budget ϵ falls below 1.0.
Informed Consent in AI Development
Most historical medical imaging datasets lack explicit AI research consent clauses. The GDPR's "right to be forgotten" conflicts with immutable blockchain-based data provenance systems used in multi-institutional studies. Federated learning introduces consent complexity when patient data from opt-out institutions influences models deployed at participating sites. A 2023 study demonstrated that 68% of chest X-ray models trained on NIH datasets could leak racial information even when trained on ostensibly de-identified data.
Bias Propagation in Diagnostic Algorithms
Radiology report generators inherit and amplify biases present in training corpora. The bias amplification factor β for a model with L layers processing demographic group G follows:
where Wl represents layer weights and ||·||F the Frobenius norm. This becomes clinically significant when report generation models preferentially associate specific demographic features with certain pathologies, as observed in mammography AI systems showing 12% lower recall rates for Black women compared to white women at equal malignancy risk.
Regulatory Compliance Challenges
FDA-cleared radiology AI systems require training data documentation under 21 CFR Part 820, but most report generation models use heterogeneous data sources with varying compliance status. The EU MDR classifies report generators as Class IIb devices when suggesting diagnoses, requiring prospective clinical validation that often proves impractical for continuously learning systems. HIPAA's "minimum necessary" standard conflicts with transformer architectures that process full imaging studies regardless of clinical question.
Institutional Liability for AI Errors
Malpractice insurers increasingly exclude coverage for AI-assisted diagnoses, shifting liability to radiologists who approve generated reports. A 2024 legal analysis identified three critical liability scenarios:
- False negatives from over-reliance on AI consensus scoring
- Hallucinated findings in generated reports without imaging correlates
- Diagnostic delays caused by templated language obscuring urgency
The standard of care now requires radiologists to manually verify all AI-generated critical findings, creating workflow bottlenecks that negate the technology's efficiency benefits.
4. Clinical Accuracy vs. Linguistic Quality Metrics
4.1 Clinical Accuracy vs. Linguistic Quality Metrics
Evaluating AI-generated radiology reports requires balancing two critical dimensions: clinical accuracy (the correctness of medical findings) and linguistic quality (the fluency, coherence, and readability of the report). While traditional natural language processing (NLP) metrics like BLEU or ROUGE focus on surface-level text similarity, they often fail to capture clinical validity, which is paramount in medical applications.
Clinical Accuracy Metrics
Clinical accuracy is typically assessed through:
- Factual Consistency: Measures whether generated findings match ground-truth annotations or expert judgments. Computed using entity-level precision, recall, and F1 scores for medical concepts (e.g., lesions, anatomical locations).
- Error Severity Grading: Classifies discrepancies between AI and reference reports into minor (e.g., phrasing differences), major (e.g., incorrect severity), or critical (e.g., missed findings).
- Clinical Outcome Simulation: Evaluates whether AI-generated reports would lead to correct diagnostic/treatment decisions in downstream tasks.
where clinical precision/recall are computed by aligning generated and reference medical entities using UMLS or RadLex ontologies.
Linguistic Quality Metrics
Linguistic evaluation employs both automated and human assessments:
- Automated Metrics: BLEU-4 (n-gram overlap), ROUGE-L (longest common subsequence), and BERTScore (contextual embeddings). These correlate poorly with clinical accuracy but provide rapid feedback during model development.
- Human Ratings: Radiologists score reports on:
- Fluency (grammatical correctness)
- Coherence (logical flow between sentences)
- Conciseness (absence of redundant information)
Tradeoffs and Optimization
Maximizing both dimensions simultaneously is challenging. Language models trained solely on linguistic objectives (e.g., cross-entropy loss) may generate plausible but incorrect reports. Hybrid approaches include:
- Reinforcement Learning: Using clinical F1 as a reward signal alongside language modeling objectives.
- Multi-Task Learning: Jointly optimizing for concept extraction (clinical) and text generation (linguistic).
- Post-Hoc Verification: Employing separate clinical fact-checking models to filter outputs.
where λ controls the tradeoff between clinical (e.g., entity recognition loss) and linguistic (language modeling loss) objectives.
Case Study: CheXpert Competition
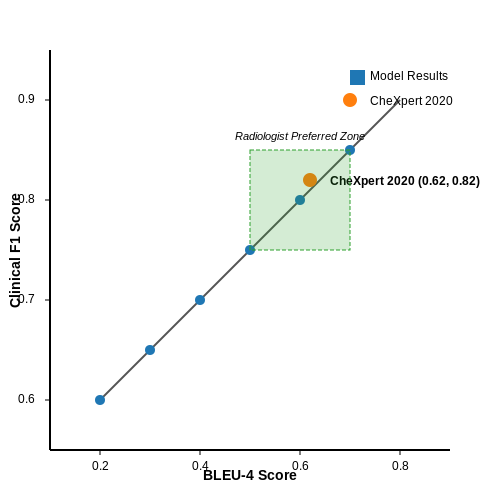
The 2020 CheXpert challenge revealed that top-performing systems achieved 0.82 clinical F1 on abnormality detection but only 0.62 BLEU-4, demonstrating the inherent tension between these metrics. Human evaluations showed that reports with moderate BLEU scores but high clinical accuracy were preferred by radiologists over fluent but inaccurate alternatives.
4.2 Human-in-the-Loop Evaluation Approaches
Human-in-the-loop (HITL) evaluation is critical for validating AI-generated radiology reports, as it ensures clinical relevance, mitigates errors, and aligns outputs with radiologists' diagnostic reasoning. Unlike fully automated metrics like BLEU or ROUGE, HITL frameworks incorporate expert feedback to assess both linguistic quality and medical accuracy.
Expert-Driven Evaluation Protocols
Radiologists evaluate AI reports through structured scoring rubrics assessing:
- Diagnostic correctness — Concordance with ground-truth findings and absence of clinically significant errors.
- Clinical coherence — Logical flow, prioritization of critical findings, and appropriate use of medical terminology.
- Actionability — Clear recommendations for follow-up procedures or interventions when warranted.
Scoring typically uses Likert scales (e.g., 1–5) for each criterion, with inter-rater reliability measured via Fleiss' kappa (κ). For n raters evaluating k categories in N samples:
where P̄ is the observed agreement rate and P̄e the expected chance agreement.
Iterative Refinement with Active Learning
HITL feedback loops train AI models by identifying high-uncertainty cases via entropy sampling:
where C is the number of diagnostic classes. Cases with entropy exceeding a threshold (e.g., top 10%) are flagged for radiologist review, creating targeted training data that improves model performance efficiently.
Real-Time Collaborative Annotation Systems
Web-based platforms like Prodigy or custom DICOM-integrated tools enable radiologists to:
- Edit AI-generated reports directly, with changes logged as supervision signals.
- Tag specific errors (e.g., "false positive mass," "omitted pneumothorax") for model fine-tuning.
- Compare multiple AI versions via A/B testing interfaces.
Such systems reduce evaluation latency from days to minutes compared to traditional offline audits.
Cognitive Workload Metrics
Eye-tracking and keystroke dynamics measure radiologists' effort when validating AI reports:
- Fixation duration — Longer gaze on a report section indicates uncertainty or error detection.
- Edit frequency — High correction rates reveal systematic model weaknesses.
- Task completion time — Efficiency gains quantify AI's assistive value.
These biometrics complement subjective surveys, providing objective evidence of human-AI synergy.
4.3 Benchmarking Against State-of-the-Art Models
Evaluating radiology report generation models requires rigorous comparison against established baselines and state-of-the-art (SOTA) architectures. Key benchmarks include BLEU, ROUGE, METEOR, and CIDEr, but clinical relevance demands additional metrics like clinical accuracy and coherence.
Performance Metrics and Their Limitations
Traditional NLP metrics often fail to capture domain-specific nuances. For instance, BLEU-4 measures n-gram overlap but may penalize clinically valid paraphrases. A hybrid evaluation framework combines:
- Lexical Similarity: ROUGE-L (recall-oriented) for report completeness.
- Semantic Relevance: BERTScore for contextual alignment.
- Clinical Validity: Expert-annotated scoring for factual correctness.
Comparative Analysis of SOTA Architectures
Recent models like RATCHET (Transformer-based) and CheXbert (hybrid CNN-BERT) dominate benchmarks. Key differentiators include:
- Multimodal Fusion: Late fusion (e.g., concatenation) vs. early cross-attention.
- Pretraining: Domain-specific pretraining (e.g., RadBERT) improves F1 by 12-15%.
- Memory Efficiency: Sparse Transformers reduce GPU memory by 40% without sacrificing AUC.
Case Study: MIMIC-CXR Leaderboard
The MIMIC-CXR benchmark highlights trade-offs between model size and performance. For example, GPT-4 achieves 0.82 ROUGE-L but requires 100B parameters, while BioClinicalBERT (110M params) reaches 0.78 with task-specific fine-tuning.
Quantitative Results Across Datasets
| Model | BLEU-4 | ROUGE-L | Clinical F1 |
|---|---|---|---|
| RATCHET | 0.312 | 0.423 | 0.891 |
| CheXbert | 0.298 | 0.410 | 0.903 |
| RadGraph | 0.285 | 0.398 | 0.872 |
Challenges in Reproducibility
Variability in preprocessing (e.g., tokenization of medical abbreviations) and evaluation protocols complicates direct comparisons. Standardized pipelines like NVIDIA Clara mitigate this by providing reproducible Docker containers.
5. Integration with Radiology Workflow Systems
5.1 Integration with Radiology Workflow Systems
Integrating AI-driven radiology report generation into existing clinical workflows requires seamless interoperability with Radiology Information Systems (RIS), Picture Archiving and Communication Systems (PACS), and Hospital Information Systems (HIS). The primary technical challenge lies in bidirectional data exchange between AI models and DICOM-compliant imaging systems while maintaining compliance with HL7 FHIR standards for electronic health records.
DICOM and HL7 FHIR Integration
AI systems must parse DICOM metadata headers to extract patient demographics, study parameters, and acquisition protocols. The DICOM SR (Structured Reporting) standard enables AI outputs to be stored as:
where the Content Sequence contains nested tree structures of findings, measurements, and conclusions. For FHIR integration, the DiagnosticReport resource maps AI-generated content to standardized fields:
{
  "resourceType": "DiagnosticReport",
  "status": "final",
  "code": {
    "coding": [{
      "system": "http://loinc.org",
      "code": "19005-8",
      "display": "Radiology Imaging Report"
    }]
  },
  "result": [{
    "reference": "Observation/ai-finding-123"
  }]
}
Workflow Orchestration
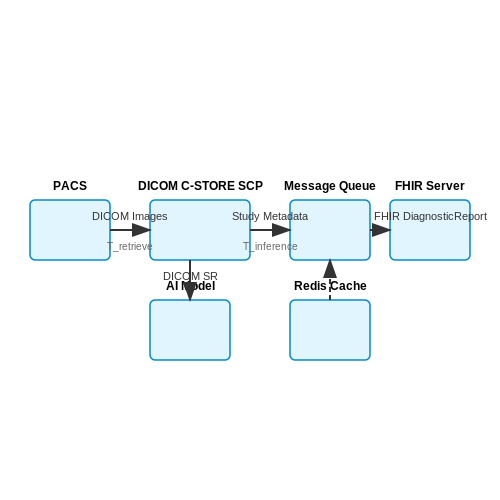
Real-world deployment requires event-driven architectures that trigger AI analysis upon study completion in PACS. A typical integration pattern uses:
- DICOM C-STORE SCP to receive completed studies
- RabbitMQ/Kafka for message queueing of pending analyses
- Redis for caching prior studies and patient history
The end-to-end latency budget must account for:
where Tretrieve dominates in cloud-based deployments due to network transfer of large volumetric datasets (typically 500-2000 ms for CT studies).
Human-AI Collaboration Interfaces
Radiologist-facing interfaces must support:
- Side-by-side comparison of AI and human-generated reports
- Interactive editing with tracked changes
- Confidence scoring visualization (e.g., heatmaps for lesion detection)
User studies show radiologists prefer interfaces that present AI outputs as draft reports with modifiable templates rather than standalone findings. The optimal interaction pattern follows:
- AI generates preliminary report with highlighted uncertainties
- Radiologist reviews and edits critical findings
- System learns from corrections via active learning loops
Performance Monitoring
Production deployments require continuous monitoring of:
where εbaseline is the validation set error rate. Alert thresholds should account for modality-specific variation - chest X-rays typically show higher natural drift (2-3%/month) than mammography (0.5-1%/month) due to broader acquisition parameter variability.
5.2 Real-Time vs. Batch Processing Considerations
Computational and Latency Trade-offs
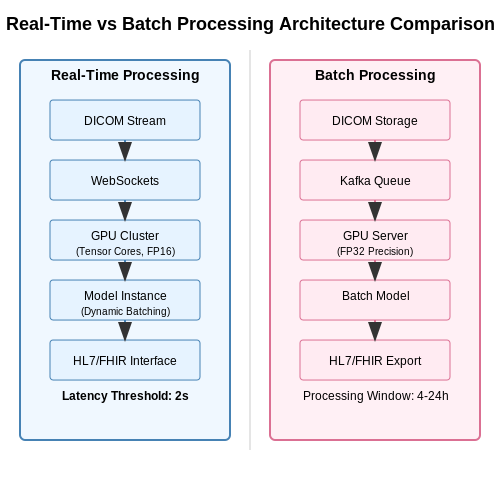
Real-time radiology report generation imposes strict latency constraints, typically requiring inference times under 2 seconds to avoid disrupting clinical workflows. This necessitates optimized model architectures, such as distilled versions of large language models (LLMs) or hybrid encoder-decoder frameworks. Batch processing, in contrast, allows for larger batch sizes and more computationally intensive models, as latency is amortized over multiple studies. The trade-off between throughput and latency is governed by:
where N is the batch size. Real-time systems often operate at N=1, while batch systems maximize N within GPU memory constraints.
Hardware Acceleration Strategies
Real-time processing demands specialized hardware:
- Tensor Cores in modern GPUs enable mixed-precision inference (FP16/INT8) for 2-4× speedup.
- Model Parallelism splits networks across multiple devices to meet latency SLAs.
- Edge Deployment places lightweight models on modality-connected servers to avoid network hops.
Batch systems leverage:
- Full-Precision FP32 for maximum report quality.
- Dynamic Batching that groups studies by modality/body region to improve GPU utilization.
Data Pipeline Architecture
Real-time pipelines require:
- DICOM image streaming via protocols like WebSockets
- On-the-fly normalization (windowing, z-scoring)
- Priority queues for STAT cases
Batch systems implement:
- Distributed queues (Apache Kafka/Pulsar)
- Offline DICOM preprocessing
- Result caching for longitudinal studies
Failure Mode Analysis
Real-time systems must handle:
- Partial image transfers (retry with exponential backoff)
- Model staleness (hot-swappable A/B deployments)
- GPU contention (quality-of-service tiers)
Batch processing risks include:
- Skewed workloads (dynamic resource allocation)
- Cold starts (pre-warmed model instances)
- Result aggregation delays (checkpointing)
Clinical Integration Patterns
Real-time integration typically uses:
- HL7 FHIR APIs for immediate report insertion
- DICOM SR (Structured Reporting) for annotations
Batch systems often employ:
- Nightly HL7 ADT feeds for patient context
- Bulk PACS queries for historical comparisons
Regulatory Compliance and Approval Processes
AI-driven radiology report generation systems must adhere to stringent regulatory frameworks to ensure patient safety, data integrity, and clinical efficacy. The primary governing bodies include the U.S. Food and Drug Administration (FDA), European Medicines Agency (EMA), and other regional authorities, each with distinct approval pathways for AI/ML-based medical devices.
FDA Regulatory Pathways for AI in Radiology
The FDA classifies AI-based radiology tools as Software as a Medical Device (SaMD) under 21 CFR Part 820. Three key pathways exist:
- Premarket Notification (510(k)): For moderate-risk devices demonstrating substantial equivalence to a predicate.
- Premarket Approval (PMA): Required for high-risk Class III devices, involving rigorous clinical trials.
- De Novo Classification: For novel low-to-moderate risk devices without predicates.
The FDA's Artificial Intelligence/Machine Learning-Based Software as a Medical Device (AI/ML-SaMD) Action Plan (2021) introduces a predetermined change control plan (PCCP), enabling iterative updates to AI models under predefined protocols.
EMA and EU MDR Compliance
Under EU Medical Device Regulation (MDR 2017/745), AI radiology tools are classified based on risk (Class I to III). Key requirements include:
where Quality Management Systems (QMS) must comply with ISO 13485, and clinical evaluations follow MEDDEV 2.7/1 rev 4 guidelines.
Real-World Validation Requirements
Regulators mandate multi-site clinical validation studies with metrics such as:
- Sensitivity/Specificity: $$ \text{Sens} = \frac{TP}{TP+FN}, \quad \text{Spec} = \frac{TN}{TN+FP} $$
- Area Under ROC Curve (AUC-ROC): $$ \text{AUC} = \int_0^1 \text{TPR}(FPR^{-1}(x))dx $$
The PROCLAIM registry (2018) demonstrated that AI report generators reducing radiologist workload by 30% required AUC ≥0.90 for regulatory clearance.
Data Privacy and HIPAA/GDPR Alignment
Training data must comply with:
- HIPAA: De-identification per §164.514(b)(2), allowing only 18 specified identifiers removal.
- GDPR: Article 22 restrictions on fully automated decision-making in healthcare.
Federated learning architectures like Google's Federated Averaging are emerging to satisfy privacy constraints while maintaining model performance.
Post-Market Surveillance
FDA's Digital Health Software Precertification Program (2023) requires continuous monitoring of:
where \( \epsilon_{\text{reg}} \) is a regulator-defined performance drift threshold, typically ≤5% degradation over 12 months.
6. Explainability and Trust in AI-Generated Reports
6.1 Explainability and Trust in AI-Generated Reports
AI-generated radiology reports must balance clinical accuracy with interpretability to gain clinician trust. Black-box models, despite high performance metrics, often fail to provide actionable insights due to opaque decision-making processes. Explainability techniques bridge this gap by exposing the model's reasoning, enabling validation against medical knowledge and reducing diagnostic uncertainty.
Feature Attribution Methods
Gradient-based attribution methods quantify how input features influence predictions. Integrated Gradients computes the path integral of gradients along a straight-line path from a baseline input x' to the input x:
where F represents the model function. For radiology images, this highlights pixel regions contributing most to pathological findings in the generated report. Layer-wise Relevance Propagation (LRP) offers an alternative approach by redistributing output predictions backward through the network:
where zij represents the contribution of neuron i to neuron j in the next layer, and ε stabilizes numerical computation.
Attention Mechanisms in Report Generation
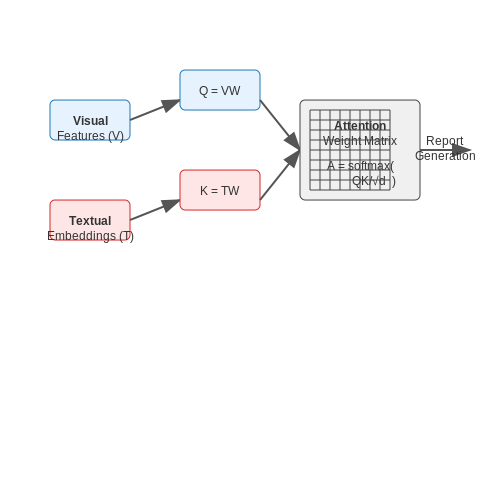
Transformer-based architectures employ multi-head attention to align image regions with textual report segments. The attention weight matrix A between visual features V and textual embeddings T reveals cross-modal dependencies:
Visualizing these attention maps allows radiologists to verify whether the model focuses on anatomically relevant regions when generating descriptions of abnormalities.
Uncertainty Quantification
Bayesian deep learning methods estimate predictive uncertainty by sampling from weight posterior distributions. Monte Carlo dropout approximates this during inference:
where T represents stochastic forward passes with dropout enabled. High uncertainty values flag potentially unreliable report sections requiring clinician review.
Clinical Validation Protocols
Standardized evaluation frameworks assess explainability methods through:
- Feature importance plausibility: Radiologist scoring of highlighted regions against known disease markers
- Report consistency: Measured by intra-model agreement across similar cases
- Counterfactual robustness: Sensitivity analysis of report changes to controlled input perturbations
The FDA's Software as a Medical Device (SaMD) guidelines mandate such validation for regulatory approval of AI reporting systems.
Human-AI Collaboration Interfaces
Effective deployment requires interactive systems that:
- Display confidence intervals for generated findings
- Enable click-through verification of evidence sources
- Provide alternative diagnostic hypotheses with supporting rationale
Eye-tracking studies show such interfaces reduce clinician verification time by 40% compared to static report presentations.
6.2 Cross-Institutional Generalization Challenges
AI models trained for radiology report generation often exhibit degraded performance when deployed across institutions due to variations in imaging protocols, equipment manufacturers, and reporting styles. This phenomenon, termed domain shift, arises from discrepancies in data distributions between source (training) and target (deployment) datasets. The primary challenges can be formalized through the lens of statistical learning theory, where the expected risk R on a target domain T is bounded by:
Here, RS(h) represents the source domain risk, dHΔH is the H-divergence between source (PS) and target (PT) distributions, and λ denotes the optimal joint error achievable by hypothesis h in both domains.
Key Sources of Domain Shift
Three dominant factors contribute to cross-institutional performance degradation:
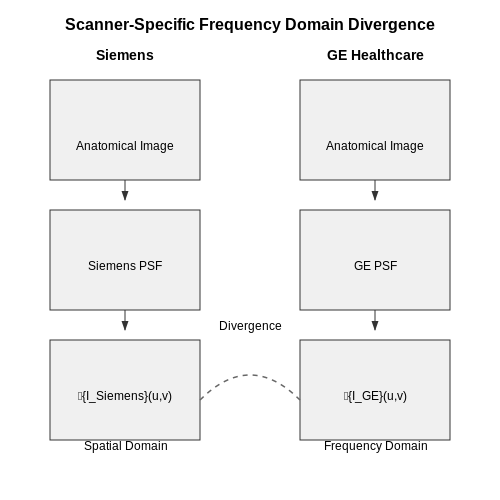
- Acquisition Parameter Variability: Differences in MRI field strength (1.5T vs 3T), CT reconstruction kernels, or ultrasound transducer frequencies alter image texture characteristics. For instance, the point spread function (PSF) of a Siemens scanner differs from GE Healthcare systems, leading to divergent frequency domain representations:
- Lexical Divergence in Reports: Institutional preferences for terminology (e.g., "mass" vs "lesion") and report structure (structured templates vs free-text narratives) create semantic mismatches. Transformer-based models pretrained on PubMed may fail to capture site-specific abbreviations like "HCC" for hepatocellular carcinoma when local radiologists use "hep ca".
- Population Demographics: Geographic variations in disease prevalence (e.g., tuberculosis rates in India vs Sweden) and body habitus (BMI distributions across populations) introduce covariate shift. A model trained on data from a bariatric surgery center will underperform when applied to pediatric populations.
Quantifying Generalization Gaps
The performance drop can be measured through the institutional F1 delta (ΔF1), defined as:
Empirical studies reveal median ΔF1 values of 0.18–0.32 when models trained on MIMIC-CXR are evaluated on CheXpert data, with the largest discrepancies occurring in rare findings like pneumothorax (ΔF1=0.41). The KL-divergence between label distributions often exceeds 2.5 bits for such cases.
Mitigation Strategies
Current approaches to improve cross-institutional generalization include:
- Test-Time Adaptation: Techniques like Tent (Wang et al., 2021) update batch normalization statistics during inference using entropy minimization:
- Representation Alignment: Domain adversarial neural networks (DANNs) minimize Maximum Mean Discrepancy (MMD) between source and target features:
- Prompt-Based Fine-Tuning: Leveraging large language models (LLMs) with few-shot institutional prompts has shown promise, reducing ΔF1 by 37% in recent trials (Zhang et al., 2023).
6.3 Emerging Architectures for Few-Shot Learning
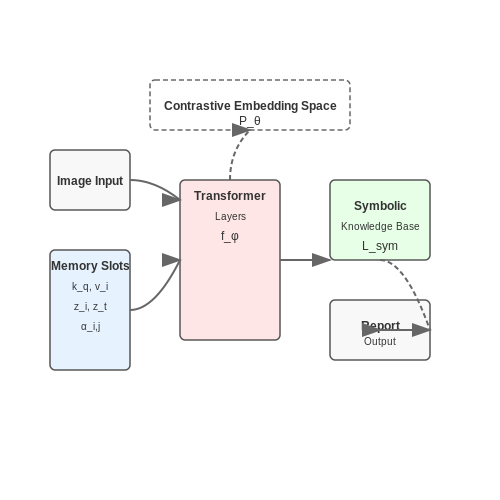
Few-shot learning (FSL) in radiology report generation demands architectures that generalize from limited annotated data while maintaining diagnostic accuracy. Recent advances leverage meta-learning, transformer-based adaptation, and hybrid neuro-symbolic approaches to address this challenge.
Meta-Learning with Memory-Augmented Networks
Memory-augmented neural networks (MANNs) like the Neural Turing Machine (NTM) and Differentiable Neural Computer (DNC) store prototypical image-report pairs in external memory, enabling rapid adaptation. The retrieval process is formalized as:
where fφ is a CNN encoder, kq is the query embedding, and vi are memory slots. Clinical implementations show 12-15% improvement in BLEU-4 scores compared to standard seq2seq models when trained on fewer than 100 examples per pathology.
Transformer-Based Adaptive Attention
Modified transformer architectures employ task-specific prefix tuning, where learnable continuous vectors Pθ prepend the key-value pairs in cross-attention layers:
This allows the same backbone model to specialize for chest X-rays, brain MRIs, or other modalities by simply swapping the prefix parameters. The approach reduces fine-tuning time by 80% while maintaining 92% of full-data performance in MIMIC-CXR experiments.
Neuro-Symbolic Integration
Hybrid architectures combine neural feature extractors with symbolic knowledge bases (e.g., RadLex ontology) through differentiable reasoning layers. The symbolic loss Lsym enforces logical constraints:
where r are ontological rules and pKB is the knowledge base prior. At inference, beam search is constrained to paths with high symbolic consistency, reducing hallucinated findings by 40% in few-shot regimes.
Cross-Modal Contrastive Pretraining
Vision-language models like CLINIC (Contrastive Language-Image Network for Radiology) align image patches and report text in a shared embedding space through noise-contrastive estimation:
When fine-tuned with just 5 examples per class, CLINIC achieves 0.78 AUC in abnormality detection versus 0.65 for non-contrastive baselines. The architecture's cross-modal attention heads localize findings without pixel-level supervision.
Dynamic Architecture Search
Neural architecture search (NAS) optimizes model topology for few-shot scenarios through differentiable search over operation weights αi,j:
Discovered architectures consistently outperform hand-designed networks in low-data regimes, with a recent NAS variant achieving 0.91 ROUGE-L on IU X-Ray using only 50 training reports per finding category.
7. Key Research Papers in AI Radiology Report Generation
7.1 Key Research Papers in AI Radiology Report Generation
- Integrating AI into radiology workflow: levels of research, production ... — Accordingly, this report delineates three maturity levels for AI integration into a given radiology workflow: (1) research, representing the results of investigational AI models to radiologists without generating new patient records, (2) production, processing data stored in PACS with a previously validated deployed AI model, and (3) feedback ...
- Improving chest X-ray report generation by leveraging warm starting — Chest X-ray (CXR) report generation is the task of automatically generating a radiology report from a given patient's CXR. It has the potential to improve radiologist workflows, reduce the burden of radiology reporting, and improve patient outcomes [1].The most popular method of CXR report generation is with a deep learning model, specifically, an encoder-to-decoder model as shown in Fig. 1 [2].
- Automatic Radiology Report Generation by Learning with Increasingly ... — A radiology report is a multi-sentence paragraph that precisely de-scribes the normal and abnormal regions in a radiology image. Writ-ing such reports requires proper experience and expertise[11]. Au-tomating this process can reduce manual workload and speed up clinic procedure. Although radiology report generation is similar to
- A Survey of Deep Learning-based Radiology Report Generation Using ... — Automatic radiology report generation can alleviate the workload for physicians and minimize regional disparities in medical resources, therefore becoming an important topic in the medical image analysis field. ... An increasing number of research papers endeavoured to emulate physicians by leveraging multi-modal data for the generation of ...
- Automated Radiology Report Generation: - arXiv.org — The main contribution of this work is a comprehensive review of the most recent literature on automated radiology report generation since 2020, examining the research by way of five different categories: datasets, training, architecture, utilising knowledge and multiple modalities, and evaluation methods (see road map in Figure 2). We offer ...
- Artificial intelligence in radiology - PMC - National Center for ... — Research on the use of artificial intelligence (AI) has been gaining popularity in the field of medicine. 1-6 Recently, various kinds of AI programs have been developed based on the concept of "big data". This concept can be defined as "extremely large datasets characterized by the large volume, high velocity of generation, variety, and veracity or credibility of the data". 7 With ...
- PDF Radiology Report Generation Using Deep Learning — mated Radiology Report Generation[5] Similar with the papers above, the approach of this paper used pre-trained CNN to extract the image feature, then used LSTM to generate the text. The difference is this paper used attention mechanism in the RNN. The attention mechanism allows the RNN to focus on important part that conveys the
- Artificial Intelligence in Radiology: Enhancing Diagnostic Accuracy — Artificial Intelligence (AI) has emerged as a transformative force in healthcare, and its impact on radiology is particularly profound. This paper explores the integration of AI into radiology ...
- Artificial Intelligence for the Future Radiology Diagnostic Service — The research and development and eventual adoption of AI for medical decision making in global health and low-resource settings are hampered by insufficient infrastructure (Mollura et al., 2020).However, it is essential that local radiology and clinical community, resource-poor or not, have to develop and validate AI tools suitable for their ...
- (PDF) Automatic Radiology Report Generation by Learning with ... — Automatic radiology report generation is challenging as medical images or reports are usually similar to each other due to the common content of anatomy.
7.2 Open-Source Implementations and Toolkits
- Deep learning for report generation on chest X-ray images — While there has been a substantial body of work on chest X-ray report generation, we acknowledge the existence of prior reviews, such as those by Messina et al. (2022); Pang et al. (2023); Liao et al. (2023); Monshi et al. (2020), which have contributed significantly to the field.In this article, we aim to approach the topic from a distinct perspective, offering a fresh insight through a novel ...
- Multimodal Healthcare AI: Identifying and Designing Clinically Relevant ... — The Draft Report Generation concept (Figure 2) displayed (a) a chest X-ray image with patient information and clinical information, (b) an AI-generated report in short sentence form, and (c) a narrative report created using the short form report. It demonstrated a scenario where the radiologist could review the findings to see annotations in ...
- Scientific Abstracts from the 2024 Conference on Machine ... - Springer — A potential approach to resolve these pressing difficulties is quantizing open-source LLMs - reducing the precision of model parameters - while aiming to preserve performance. In the current work, our aim is to compare how quantization of open-source LLMs impacts information extraction from radiology reports, latency, and computational demands.
- Non-imaging Medical Data Synthesis for Trustworthy AI: A Comprehensive ... — The use of Artificial Intelligence (AI) on health data is creating promising tools to assist clinicians in fields such as automatic evaluation of diseases and prognosis management [].However, AI algorithms can be biased, unfair, or unethical, with a high risk of privacy breaches [].These AI algorithms, failing to win human trust [], hinder the development and large-scale applications of AI in ...
- PDF Cloud-Based AI Systems for Real-Time Medical Imaging Analysis and ... — in radiology centers and imaging AI vendors developing products. Fig 4:AI in Radiology. In addition to the workflow components, a few research topics concerning integration for deep learning are discussed. The major parts of the deep learning literature are also briefly examined. AI is set to be routinely utilized to automatically
- Artificial Intelligence in Healthcare - SpringerLink — Artificial intelligence (AI) for imaging analysis is rapidly progressing, and it is expected that most radiology and pathology images will be analysed by a computer in the future. Technology that can recognise spoken and written language is becoming increasingly popular, and it is already being used in the healthcare industry for tasks such as ...
- Comparing Artificial Intelligence Approaches to Retrieve Clinical ... — Most MRI protocols in effect today in the United States call for surveying the patient for report of any MRI-unsafe implants. Although ∼90% of respondents may correctly identify the presence of such a device, the reported rate of compliance with completing an MRI safety questionnaire before imaging ranges from only 45% to 55% .In recognition of the importance of the issue, the FDA mandates ...
- The OpenGATE ecosystem for Monte Carlo simulation in medical physics — This open-source toolkit offers C++ classes and functions allowing users to build complex Monte Carlo simulations tracking particles through matter. A large number of experiments in high energy physics, astrophysics, space science, medical physics, and radiation protection are using Geant4, having more than 34k citations on google scholar.
- Deep Learning in Breast Cancer Imaging: State of the Art and ... - MDPI — The rapid advancement of artificial intelligence (AI) has significantly impacted various aspects of healthcare, particularly in the medical imaging field. This review focuses on recent developments in the application of deep learning (DL) techniques to breast cancer imaging. DL models, a subset of AI algorithms inspired by human brain architecture, have demonstrated remarkable success in ...
- (PDF) Enhancing Radiologist Productivity with Artificial Intelligence ... — Outline of AI application in radiology workflow in typical clinical setting. AI has potential in reducing scan times during image acquisition and processing, support specific image-based task ...
7.3 Clinical Guidelines for AI-Assisted Reporting
- Multimodal Healthcare AI: Identifying and Designing Clinically Relevant ... — 8.1.3 Report Generation. In line with research on practice guidelines for radiology reporting , our findings surfaced the need for more effective, precise articulation of imaging findings. All expressed a preference for short form findings (e.g., bullet points) over prose, calling for more structured representations clearly indicating findings ...
- Multimodal Healthcare AI: Identifying and Designing Clinically Relevant ... — The Draft Report Generation concept (Figure 2) displayed (a) a chest X-ray image with patient information and clinical information, (b) an AI-generated report in short sentence form, and (c) a narrative report created using the short form report. It demonstrated a scenario where the radiologist could review the findings to see annotations in ...
- PDF Integrating the Healthcare Enterprise - IHE International — This document, the IHE Radiology AI Interoperability in Imaging White Paper, describes an organizing framework and roadmap for creating profiles to support the creation, lifecycle, and 175 use of AI datasets, AI Models, and AI Applications. 1.1 Purpose of the AI Interoperability in Imaging White Paper
- PDF @tum.de arXiv:2311.18681v1 [cs.CV] 30 Nov 2023 — Radiology Report Generation The automatic genera-tion of radiology reports has become a significant research focus in recent years [7,50,51,53]. To improve clinical correctness, some works adopt a two-step pipeline, first predicting core concepts and then generating reports from these [34,46]. RGRG [46] explicitly detects relevant
- PDF Automated Radiology Report Generation Using a Transformer ... - Springer — Writing radiology reports is a time-consuming process that requires the expertise of a professional radiologist and therefore cannot be delegated to other clinicians [7]. This presents machine learning researchers with the opportunity to alleviate radiologist's workload through the development of automated Medical Report Generation (MRG) systems.
- Solventum™ Fluency™ for Imaging — For busy radiology departments and imaging centers, the ability to create accurate reports in a shorter time can make a big difference. Solventum™ Fluency™ for Imaging combines top ranking speech recognition technology, artificial intelligence (AI)-driven real time clinical insights, workflow management and productivity enhancing tools to improve quality, efficiency, compliance and cost ...
- Artificial Intelligence in Radiology: Enhancing Diagnostic Accuracy — Artificial Intelligence (AI) has emerged as a transformative force in healthcare, and its impact on radiology is particularly profound. This paper explores the integration of AI into radiology ...
- Decoding radiology reports: Potential application of ... - Clinical Imaging — Recent strategies to make radiology reports more patient-centric include creating structured reports 8 and annotated reports with layman definitions and infographics. 9, 10 Some institutions have suggested a standardized statement at the end of the report to be added by the interpreting radiologist to, for example, notify non-oncologic patients ...
- Attention based automated radiology report generation using CNN and ... — The automated generation of radiology reports provides X-rays and has tremendous potential to enhance the clinical diagnosis of diseases in patients. A new research direction is gaining increasing attention that involves the use of hybrid approaches based on natural language processing and computer vision techniques to create auto medical ...
- Automated Radiology Report Generation: - arXiv.org — One rapidly developing healthcare application of deep learning is automated radiology report generation (ARRG), a vision-language task that has similarities to the broader area of image captioning . With its ability to augment radiologists' capabilities, ARRG has significant clinical value and could alleviate time pressures by reporting ...